Medical News Blog Information

Showing posts with label Sierra Leone. Show all posts

Snapdate: Ebola virus diseaseClick on image to enlarge.

This is one of the data visualizations from my Ebola virus disease (EVD) graphs and tallies page.[1]

A crude extrapolation from current publicly available Ebola virus disease (EVD) confirmed case numbers. To see how I made this please visit here.[2]
The P-value for this linear trend model is <0.0001. 
The standard error = 6.13; R-squared = 0.20.
Click on graph to enlarge.
The first time I posted it I wondered if the end was in sight. That was 6th of May. Over three months later I'm wondering that again - but this time things are a bit different. There has been a steady decline in new cases, also in cases that cannot be tracked back to a known source and in cases found only after they have died of EVD. There have also been the first very promising results from one of the vaccine candidates in Guinea [4] - which has always been a difficult locale for the control of EVD case activity.

So it does look much more likely that the end to EVD in West Africa, or at least an end, is nigh.

By "an end" I mean that we may be close to seeing the cessation of new cases popping up in transmission chains each and every week. We may soon be seeing zero new cases for long periods of time. Those blissful stretches however, may be punctuated by a case arising from parts unknown. They may be tracked to a sexual transmission event, or their origin may never be fully understood. We saw this scenario in Liberia.[3] Virus characterisation indicated that the Ebola virus variant from the young Liberian man was most closely resembled other viruses that had been circulating in Liberia weeks before; the exact source of his infection though, remains unknown.

So we're not at all free and clear of this virus yet - but we are getting very close to shifting into another phase. It's still a long haul with many weeks of anxious waiting and heightened vigilance as well as the need to retain the capacity to cope with a new case or cases. But that said, we do seem to have taken one more step back from the precipice we once stared into as we imagined an Africa fending off a rolling EVD epidemic - and a world at risk as well - however unlikely that should have been. 

Ebola virus disease: obliterating a variant and stalled case decline...

We've seen the words vigilant and vigilance used widely in recent weeks, ever since we entered a "new phase" of the Ebola virus disease (EVD) battle/fight/war.

The reason for vigilance in all things to do with this campaign has become obvious as the weeks have passed; the reduction in cases has stalled.

I've very crudely drawn in some trends below. Whether you agree with them or not, it is clear that since the fast fall in confirmed cases reported between November-January, it seems to have become very difficult to stamp out the last fires of EVD. 

The phases.
(Very) rough trends in the number of EVD cases over time.
Date from World Health Organization situation reports (SitReps)
and situation summaries (SitSumms).
Click on image to enlarge.
Liberia has come the closest to completing this goal of obliterating the Makona variant of the Zaire ebolavirus (EBOV|Makona) with just 3-9 confirmed cases between World Health Organization (WHO) Situation Report (SitReps) during any of the past 7 weeks. It seems that recent cases can be traced to known transmission chains too and that means no surprise outbreaks. 

However, the people of Guinea and Sierra Leone have not quite got the messages that those in Liberia seem to have embraced (without touching!) so admirably. 

In the last WHO SitRep [1] it was noted that 39-45 unsafe burials (probably not all that occurred) occurred in a week and >40 EVD cases were identified post-mortem. This last observation means exposure of the community to virus, not getting help and treatment for ill people, and unnecessarily requiring contact tracers to play catch-up. Bad for the infected people their friends and families and the response to EVD. It doesn't have to be that way.

This paints a picture of  problems with Ebola outreach and education, communication and cooperation. Those things will keep the latest EVD "phase" chugging along. 

We do need to destroy this variant of Ebola virus by isolating it in the last human cases in each of Guinea, Liberia and Sierra Leone. Once those people recover, or regrettably die, EBOV|Makona will be gone, except for what's in lab freezers around the world and in sequence databases thanks to the efforts of a few expert research teams. Once gone from "the wild", the evolutionary clock resets back to the EBOV variants in the animals of the forest.

EBOV|Makona knows too much; it has seen too much; it has learned too much, to be allowed to "live". It has been passed through humans too many times and while there is a vanishingly small chance it will sprout wings, it is still a virus that spreads relatively easily under the right conditions and circumstances. Explosive loss of 8 litres of fluids a day provides many ways to pass along this blood/gastro virus. EBOV|Makona may also have adapted, and continues to adapt, in other ways that would mean its stay among humans becomes lengthy and its dissemination more widespread.

More bad news from an unsuccessful obliteration of EBOV|Makon-smouldering EVD in Sierra Leone and Guinea may release new case embers that drift across borders and set new fires in other countries. We don't need hundreds of cases a day for that to happen.[3] We know cases also fly with the aid of planes (not wings). And the cycle could renew. I don't think we'll see such big outbreaks of EBOV|Makona again, for reasons I laid out here, but chasing new fires is more work than stamping out the remnants of old ones. Vigilance and action. 

I think vaccines still have an important role to play in the final phase of this epidemic, even if only 3 new healthcare worker cases were noted in the past SitRep week. Vaccine given to more than just healthcare workers could be useful here, if others will accept the needle.

  • Ebola outreach
  • Education
  • Communication
  • Cooperation

Oh, and vigilance.

References..

  1. http://apps.who.int/ebola/en/ebola-situation-report/situation-reports/ebola-situation-report-18-february-2015
  2. http://newsmedicalnet.blogspot.com.au/2014/08/behind-naming-of-ebola-virusesnot-yet.html
  3. http://newsmedicalnet.blogspot.com.au/2015/02/cases-of-ebola-virus-infection-can-be.html

Cases of Ebola virus infection can be exported any old time...

I'm adding my two cents on the issues around remaining vigilant about Ebola virus disease (EVD) cases. 

There are far fewer weekly EVD cases than there used to be but it remains absolutely essential to "kill off" this particular highly-passaged Zaire ebolavirus variant. In other words, push new cases down to zero per day in all three countries, keep it there for 42-days, and thus declare all three nations free of Ebola virus transmission.

Apart from the obvious desire to see these countries rid of this horrible and deadly pestilence, another, less likely thing to consider is that more spillovers to other countries can still happen at any time. And apart from the costs, the reaction from a certain country to its first imported case, just does not bear living through again.

Whether human cases were just kicking off, or after they began accruing at an exponential rate of hundreds per day, the hotspot countries have been the source of export of a case to another country. 

That said, in my opinion we are in a much better global position today than we were six to twelve months ago. We can much more effectively engage and thwart the spread of infection from an EVD case that appears on our doorstep because we now know Ebola virus is out there and can hop on a plane, and many countries and regions within countries have done something to prepare for that rare arrival. Some countries were already in a better position than others, simply because they have (relatively) huge healthcare 
processes in place and are now aware of how to help, and how quickly to respond, should a foreign neighbour acquire a case. 

None of that is to say zero spread in other countries is a given in the near future; humans being humans, accidents and mistakes will always happen. But we are just very unlikely to see EVD spread in a new country to the extent that we saw last year. Hopefully I'm not being too naive on that call.

If we look at the images below, it's plain to see that EVD cases were exported from these countries both early on and late in the outbreaks and later epidemic. Guinea being slightly more of a culprit than the other two countries of intense and widespread transmission (Liberia and Sierra Leone).

Guinea's Ebola virus disease experience. The approximate time at which 
another country receives a person infected by Ebola virus, most likely acquired
from within Liberia, are indicated by an arrow.
Click on graph to enlarge.
Sierra Leone's Ebola virus disease experience. The approximate time at which 
another country receives a person infected by Ebola virus, most likely acquired
from within Liberia, are indicated by an arrow.
Click on graph to enlarge.


Liberia's Ebola virus disease experience. The approximate time at which
another country receives a person infected by Ebola virus, most likely acquired
from within Liberia, are indicated by an arrow.
Click on graph to enlarge.


The filovirus tree has been shooting wildly

While there are not a lot of new branches, there are many, many new leaves on this growing tree. That is overwhelmingly due to the fantastic work of Dr Pardis Sabeti, and Stephen Gire at the Sabeti lab, Harvard University, and their many collaborators. 

It sounds like even more sequences will be coming out in the future. This group is the face of the molecular epidemiology of history's largest Ebola virus disease epidemic in Sierra Leone. If a team of scientists could be said to embody an aspect of an epidemic, it has been these guys and their virus characterization. Hugely impressive stuff.

I only wish we could see more Guinean and Liberian sequences - they are both hugely under-represented in this tree of complete genomes downloaded from GenBank a week or so ago.

Click on tree to enlarge even further.
Coloured boxes surround those sequences generated during the
2014 EVD epidemic. Orange boxes point out the nearest neighbours
and the year from which the sample that was sequenced, originated.
The West African Ebola virus Makona variant has been
traced back to sharing an ancestor in common with a 2007
variant in 2004.

References
  1. Genomic surveillance elucidates Ebola virus origin and transmission during the 2014 outbreak. Gire SK, Goba A, Andersen KG, Sealfon RS, Park DJ, Kanneh L, Jalloh S, Momoh M, Fullah M, Dudas G, Wohl S, Moses LM, Yozwiak NL, Winnicki S, Matranga CB, Malboeuf CM, Qu J, Gladden AD, Schaffner SF, Yang X, Jiang PP, Nekoui M, Colubri A, Coomber MR, Fonnie M, Moigboi A, Gbakie M, Kamara FK, Tucker V, Konuwa E, Saffa S, Sellu J, Jalloh AA, Kovoma A, Koninga J, Mustapha I, Kargbo K, Foday M, Yillah M, Kanneh F, Robert W, Massally JL, Chapman SB, Bochicchio J, Murphy C, Nusbaum C, Young S, Birren BW, Grant DS, Scheiffelin JS, Lander ES, Happi C, Gevao SM, Gnirke A, Rambaut A, Garry RF, Khan SH, Sabeti PC.
    Science. 2014 Sep 12;345(6202):1369-72. doi: 10.1126/science.1259657. Epub 2014 Aug 28.

WHO Media Release: Sierra Leone reacts swiftly in the face of desperate need

I am reprinting in full, with permission, what I think is a really well written "story behind the numbers". These stories provide invaluable context around the various individual human and community tragedies that are constantly occurring during this epidemic. They also highlight the many difficulties faced by those trying to help people, track and contain spread and and collate all the numbers. Those numbers may be dispassionate in their quantification of aspects of the epidemic, but they are so important to guide timely aid to the right areas and at the right scale

Freetown � 10 December 2014 - Racing to fact check an ominous spike in Ebola cases from the remote diamond district of Kono in eastern Sierra Leone, bordering Guinea, a World Health Organization rapid response team found a worse-than-expected scene. WHO and the U.S. Center for Disease Control (CDC) joined forces with the Sierra Leone National Ebola Response Center (NERC) and Ministry of Health and Sanitation (MoHS) to sound the alarm and are now rallying all-comers in a massive build up to contain this burgeoning Ebola outbreak which ran the risk of continuing to grow and remaining hidden as world attention focuses on urban centers.

�Our team met heroic doctors and nurses at their wits end, exhausted burial teams and lab techs, all doing the best they could but they simply ran out of resources and were overrun with gravely ill people,� explains Dr Olu Olushayo, WHO National Coordinator, Ebola Epidemic Response. �In districts like Kono, with moderate transmission confined to limited villages and chiefdoms, the best chance of eliminating transmission is through aggressive and comprehensive case investigation and contact tracing,� he said. Scattered villages in 8 of the 15 chiefdoms are affected.

Reacting on intel from the Ministry of Health of Sierra Leone, WHO sent a seasoned field epidemiologist to Kono 10 days ago to tease out whether reported Ebola cases told the whole story. Cases go unreported for a variety of reasons and are exacerbated when overwhelmed and under-resourced frontline workers are unable to reach remote areas to get the truth from reluctant villagers. The surveillance officers had no vehicles. WHO and CDC quickly sent more investigators and rugged trucks.

They uncovered a grim scene. In 11 days, 2 teams buried 87 bodies, including a nurse, an ambulance driver, and a janitor drafted into removing bodies as they piled up at the only area hospital, ill-equipped to deal with the dangerous pathogen. In the 5 days before the team arrived, 25 people died in the hastily cordoned off section of the main hospital serving as a makeshift Ebola holding center.

As of 9 December 2014, this district of over 350 000 people officially has 119 reported cases. Upon hearing the WHO findings, Dr. Amara Jambai, MoHS Director of Disease Prevention and Control harkened a local saying to describe what remains yet to be discovered, "we are only seeing the ears of the hippo."

Help is arriving daily. The NERC and MoHS for the Government of Sierra Leone and UNMEER with WHO support are connecting ready-to-help partners with an all-out multi-agency response to critical needs on the ground. WHO field staff are sharing their expertise with surveillance investigators, community mobilizers, infection controllers, and coordinators. The doctors from Partners in Health and Wellbody Alliance who supported the overwhelmed holding center, are willing to stay on board to support care at the source in outlying health posts. The International Federation of the Red Cross will build a new Ebola Treatment Center on a tight timetable, while they disinfect the hospital with MoHS and create a temporary safe holding unit. The IFRC Kenema Ebola Treatment Center will take Kono patients until these solutions are in place. CDC has staff on the ground. UNMEER has lent it�s helicopters to the effort in support of the UN family (WHO, UNICEF, UNFPA, WFP, and others) engaged in building up capacity for staff and volunteers through training, materials and logistical support. International Rescue Committee is supporting infection prevention activities in the district. Funders such as DIFD and USAID are making much of the fast response possible. The race is on in this frontier fight against the virus, as Ebola responders dash to get ahead of the epidemic rather than chasing its tail.


The fifth I give you...[UPDATED]

Senegal. 
According to it's Minister of Health, Awa Marie Coll Seck[1,2], a case of Ebola virus disease (EVD) has been imported from Guinea and it is confirmed by testing at the World Health Organization's collaboration Centre, the Pasteur Institute in Dakar.


Interesting that this occurred one week after Senegal closed its borders (again) with Guinea.[3,4] The infected 21-year old Guinean student travelled on 21-August to Dakar. On the 23rd he presented to a hospital but did not admit to being in contact with known EVD cases; Guinea issued an alert that a person with EVD contact has escaped surveillance 27-Aug; Senegal closed its borders around 22-August.[5,6,7,8].
[WHO Disease Outbreak News places his movements ahead of the closure of the border, arriving in Senegal 20-Aug [8]]

These borders are leaky and so the effect of "closure" essentially hinders aid, trade and economy (all very important to the region, especially right now) but very clearly does may not stop the spread of human hosts-as we have seen here. 


Humans are the variable in outbreaks. 


They behave differently each time. 


They respond differently each time. 


This is why no two outbreaks are identical. 


It's why you're a mug to assume this outbreak will be like the last outbreak.


While it looks like this is now a case study in why closing a border is ineffective, I maintain a position that border closures can't contain infectious disease. And please, do not point me to "temperature measurement" as a way to ensure capture of infected individuals. You could easily be harbouring an infection that does not yet express the symptom of fever. 

Click on image to enlarge. 
Graphic lifted from a great CNN video narrated by
Dr Sanjay Gupta. The video describes an example of
contact tracing and its importance to the fight
to contain EVD.[2] 

The contact tracing starts in Senegal now. A 42-day clock starts for the country and a signs and symptoms watch continues on all this case's contacts for 21-days.

References...
  1. http://in.reuters.com/article/2014/08/29/us-health-ebola-senegal-idINKBN0GT1CD20140829?feedType=RSS&feedName=health&utm_source=dlvr.it&utm_medium=twitter&dlvrit=309303
  2. http://edition.cnn.com/2014/08/29/health/ebola-outbreak-senegal/
  3. http://www.washingtonpost.com/news/world/wp/2014/08/29/the-ebola-virus-has-spread-to-senegal-as-the-deadliest-outbreak-in-history-gets-worse/
  4. http://www.washingtonpost.com/world/africa/alarm-grows-as-ebola-outbreak-spurs-more-flight-cancellations-border-closures/2014/08/25/87e6d020-2c66-11e4-994d-202962a9150c_story.html
  5. http://www.bbc.com/news/world-africa-28893835
  6. http://fox59.com/2014/08/22/senegal-closes-its-borders-with-guinea-over-ebola-fears/
  7. https://www.internationalsos.com/ebola/index.cfm?content_id=434&language_id=ENG


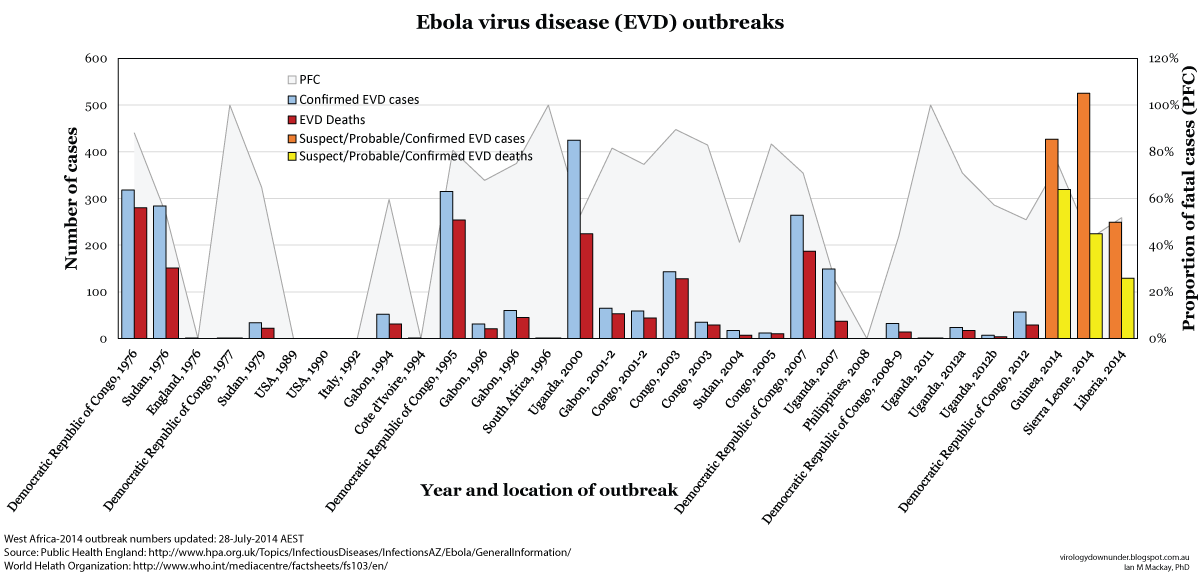
Ebola West Africa numbers in context...[AMENDED]

A quick glance at how the suspect, probable and laboratory confirmed (susp/prob/conf) cases of Ebola virus disease (EVD) stack up in the 3 countries with local spread of Zaire ebolavirus.

Please note that I have separated Guinea-2014, Sierra Leone-2014 and Liberia 2014 only to highlight that each country in the single "West Africa" outbreak (involving a single viral variant as far as we know) has greater case numbers than those found in many of the earlier outbreaks.

I have not yet listed the case imported to Nigeria here.

Click on chart to enlarge.

When 2 - 2 = 2: Ebola case numbers in Sierra Leone

I've been having a little trouble following some aspects of the World Health Organization's (WHO) updates on the Zaire ebolavirus outbreak. There have been a few things - tiny little things - that have made it more confusing for a simple chap like me to track. One of them follows.

Don't get me wrong; this is not a criticism of the fantastic job the social comms team (@HaertlG, @setiogi and @MonikaGehner and no doubt many others I am completely ignorant of) have been doing. I've openly congratulated these guys before, and do so again here; they get so much information out on so many topics to so many endpoints...staggering. The 2014 #ebola communication has been an stunning process/event/big-word-full-of-respect-awe-and-bigness to behold from the outside looking in. It should be a shining example of a multifaceted social media education, updating and mobilisation campaign.

Tonight however, I write about the case numbers from Sierra Leone...and I'm essentially "typing out loud" to work through my confusion here so I forgive you for reading no further.

Lets go back (wavy hands)...


Ebola virus disease, West Africa � update

WHO, 01-Apr-14
The Ministry of Health of Sierra Leone is maintaining a high level of vigilance following the deaths of 2 probable cases of EVD in one family who died in Guinea and their bodies repatriated to Sierra Leone. To date, active surveillance activities have identified no new suspected cases and all contacts of the deceased have remained well.
http://www.who.int/csr/don/2014_04_01_ebola/en/


Ebola virus disease, West Africa � update
WHO, 02-Apr-14
There has been no change in the situation in Sierra Leone following the deaths of 2 probable cases of EVD in one family who died in Guinea and their bodies repatriated to Sierra Leone. As this is a rapidly changing situation, the number of reported cases and deaths, contacts under medical observation and the number of laboratory results are subject to change due to enhanced surveillance and contact tracing activities, ongoing laboratory investigations and consolidation of case, contact and laboratory data.
http://www.who.int/csr/don/2014_04_02_ebola/en/


Ebola virus disease, West Africa � update

WHO, 05-Apr-14
There has been no change in the situation in Sierra Leone following the deaths of 2 probable cases of EVD in one family who died in Guinea and their bodies repatriated to Sierra Leone. The office of the Chief Medical Officer (CMO) is coordinating all operations involving suspected cases of Ebola as well as the follow-up investigations. Enhanced surveillance and public education activities are continuing.
http://www.who.int/csr/don/2014_04_05_ebola/en/


Ebola virus disease, West Africa � update

WHO, 07-Apr-14
There has been no change in the epidemiological situation of EVD in Sierra Leone. The Ministry of Health and Sanitation of Sierra Leone has confirmed that 2 suspected cases of viral haemorrhagic fever are laboratory confirmed as Lassa fever which is endemic in Sierra Leone.
http://www.who.int/csr/don/2014_04_07_ebola/en/

Ebola virus disease, West Africa � update
WHO, 10-Apr-14
Although the epidemiological situation in Sierra Leone remains unchanged, the Ministry of Health and Sanitation (MOHS) continues to lead intensive EVD preparedness activities.
http://www.who.int/csr/don/2014_04_07_ebola/en/


Okay. Cool. So what was all that for?

WHO's super-human Tweeter and communicator, Gregory H�rtl (also called Head of Public Relations/Social Media for the WHO) posted a Tweet today...

What I didn't understand was where these 2 cases from Sierra Leone had come from? See-toldya I was a simple chap.

So by listing them out, it seems they must be the 2 suspected cases - highlighted in yellow in the 07-Apr update above. 

They were 2 cases distinct from the the 2 fatal EVD cases in Sierra Leone. As it turns out those 2 fatal cases will forever remain "probable EVD cases" because they died and were not sampled. As Gregory Hartl Tweeted...
If you'd like to read more of a timeline about these two - have a look at a very detailed analysis prepared by Cedric Moro (@Moro_Cedric).

This case study also confirms that at least some of the EVD cases will not ever be getting a laboratory confirmation as I wondered about in my Ebola virus sampling issues post 09-Apr. Not only do EVD case numbers change, occasionally in slippery ways, but there are also occasions when they won't ever change despite us wanting them too. If I was a pedant this could drive me to insane.

Ebola virus disease (EVD) outbreak in West Africa: chart of cases to 04-Apr

Data are based on WHO DONs, French Embassy Conakry
 figures and WHO Tweeted information.
Click on image to enlarge.
The Ebola virus disease (EVD) case chart adjacent is based on the latest Disease Outbreak News (DON) from the World Health Organization (WHO) posted at the Global Alert and Response (GAR) site [1] and at the African Regional Office (WHO-AFRO) [2].

There are roughly 163 suspected, probable and laboratory-confirmed cases including 95 deaths (58.3% proportion of fatal cases) for which only 56 (34.4%) have been confirmed by laboratory tetsing.

I'm also maintaining a curated Storify timeline here which lists some key Tweets and links on this outbreak. 

A few things to note about the chart and the outbreak:

  1. The susp/prob/conf (shorthand I use on Twitter) numbers change - the 1st 2 numbers can go down as well as up as cases that cannot be laboratory confirmed as due to EVD are discarded from the tally. Other diseases with similar presenting signs and symptoms occur in the West African region so this is not at all unexpected. We see the same thing for other viral outbreaks, like influenzavirus, all the time.
  2. The WHO does not posted "grand totals". The DONs present totals for each region (currently Guinea, Sierra Leone and Liberia), which I've tallied up above.
  3. Its worth remembering that this outbreak was happening back in early Feb, so there was a passage of time during which people were exposed and did not know precisely what was causing illness. This creates a lag between the time of the first announcement and when the situation can come under some semblance of control. Control requires that the various teams arrive, are coordinated and set up in the area to test, trace, educate and reduce virus spread. Each time a new region has a case, the same flurry of activity may well ensue, so case numbers will seem suddenly spike - but as we can see, they do not continue to rise exponentially, or even at all in some regions. This is thanks to the expert teams including those from the WHO, jurisdictional Ministries of Health, UNICEF, the Red Cross and M�decins Sans Fronti�res (apologies to all those I've missed - you are all doing a fantastic job under extreme conditions and you are extremely  appreciated)
  4. Posts on this outbreak do not occur daily - I presume, as for avian influenza virus outbreaks etc, posting of numbers is based on when those data are collated, summarized and provided to the WHO.
  5. There are reports of 4 haemorrhagic fever cases from Mali (some of whom had traveled to Guinea; a suspect case is also reported in Ghana coming from Mali although there are questions about where from precisely) that are not, at writing, laboratory confirmed.[5] Samples are being sent to the United States for confirmation. Why not to the Institute Pasteur in Dakar, or Guinea field labs I do not know; presumably because of pre-existing arrangements?
  6. Liberia has 1 suspected EVD case in a hunter who seems to have acquired his infection locally (no contact with know EVD cases or with Guinea). This suggests to me that the vector is actively infected in the region. Perhaps this is a migratory season (seasonal change, following food sources, breeding) for this Ebola virus's animal hosts, previously found to be fruit bats, chimpanzees, gorillas, monkeys, forest antelope and porcupines in particular, eaten as "bushmeat". I admit to knowing nothing about animal movement in the region however.
  7. While EVD is "highly contagious", close contact with an infected animal host or an infected human cases' bodily fluids (blood, organs, mucous, urine, vomit, faeces and semen for up to 7-weeks post-infection) is required to acquire an infection. Generally the virus doesn't spread across distance as well or quickly as for example, influenzavirus does. This is largely because the virus is not spread the same way:
    • Sneezing and coughing is not considered a method of EVD transmission
    • Once the patient is symptomatic, they do not move around as much; from that point, spread of the virus to new people requires those people to come to the ill person. This is why healthcare workers, especially early on in an uncharacterized outbreak, and close family members caring for an ill or deceased relative number highly in new cases of EVD. 
    • Basic levels of infection prevention and control can interrupt transmission. These include good hand hygiene, use of personal protective equipment and prevention of needle stick injuries.
  8. Airborne transmission is not considered a risk factor for acquiring EVD; this is not the movie Outbreak where the fictional "Motaba" virus mutates into an airborne ebolavirus-like pathogen. Also unlike the movies, bleeding from orifices and the skin can occur, but much more rarely than the movies lead us to believe
  9. EVD signs and symptoms start suddenly 2-21-days (8-10 more common[3]) after virus acquisition and usually include fever, headache, joint and muscle aches, weakness, diarrhoea, vomiting, stomach pain, loss of appetite and may also include rash, sore throat, red eyes, hiccups, cough, chest pain, breathing and swallowing difficulties and sometimes internal and external bleeding. Not everyone dies from infection however the higher end of the mortality spectrum for the species Zaire ebolavirus can reach 90% in outbreaks with >1 case identified.[4]
  10. A person with no signs or symptoms of disease is not considered contagious.
  11. While a border closure (Senegal) and some flight restrictions have come into play, these may only serve to disadvantage the outbreak region rather than provide any true risk mitigation. Closing a border may hinder the flow of food, medical supplies and daily goods as well as interrupting the normal commerce of the country, impacting both economically and directly on the lives of the overwhelming majority of people who are not infected. I'm not aware of any evidence that shows closing a border has any reducing effect on an Ebola outbreak. Closures are a knee-jerk reaction caused by the fear of a scary disease.
And that last point is an important one. Ebola evokes some scary images outside of Africa. And so it's important for us not to run around like a decapitated Gallus gallus domesticus. We need to rein in the excessive over-reaction. As Maryn McKenna aptly noted recently over on Superbug, many things are killing more people, more regularly every day both in and outside of Africa. Having said that, I can totally understand the reactions of those living inside of West Africa just now. Among them, those who both have or have never looked this pathogen in its filovirusy-eye and stared down the barrel of its disease before. 

Viruses can be pretty scary things indeed.

References..
  1. WHO Global Alert and Response (GAR) Disease Outbreak News (DONs) Articles
    http://www.who.int/csr/don/en/
  2. WHO African Regional Office (WHO-AFRO)
    http://www.afro.who.int/en/media-centre/pressreleases.html
  3. Signs and symptoms of EVD or Ebola haemorrhagic fever (HF) from US Centers for Disease Control and Prevention
    http://www.cdc.gov/vhf/ebola/symptoms/index.html
  4. WHO EVD fact sheet
    http://www.who.int/mediacentre/factsheets/fs103/en/
  5. WHO AFRO EVD West Africa SitRep for 4-April-2014
    http://www.afro.who.int/en/clusters-a-programmes/dpc/epidemic-a-pandemic-alert-and-response/outbreak-news/4079-ebola-virus-disease-west-africa-5-april-2014.html
  6. A Patient in Minnesota Has Lassa Haemorrhagic Fever. (Don�t Panic.)
    http://www.wired.com/2014/04/minnesota-lassa/

Like Us

Blog Archive