Medical News Blog Information

Showing posts with label Kingdom of Saudi Arabia. Show all posts

MERS-CoV jumps a flight to South Korea...but from where?

It could be Qatar, Bahrain, the United Arab Emirates (UAE) or the Kingdom of Saudi Arabia (KSA). Any of these may have been the country of origin for the infected person who returned with a bunch of microscopic passengers, to the 24th country to host a case of Middle East respiratory syndrome coronavirus (MERS-CoV) infection - South Korea. 

The infected man then passed the spiky parasites on to his 63-year old wife and to a 76-year old man with whom he shared his hospital room. Close contact. From what we know of the MERS-CoV - it's a pretty ineffective transmitter among us humans types, preferring instead to give the hump to dromedaries.

Qatar seem less likely as it appears to have only been an airport transit point. If it's Bahrain, then we have 25 countries as Bahrain has not yet reported a MERS-CoV positive person. Both the people and the camels of the UAE and KSA are well known to this virus both in humans and camels. 

We await the clarity of the World Health Organization's analysis in a Disease Outbreak News (DON) article - although this might be a tough one to unravel.

Click on image to enlarge.

Where did the MERS-CoV comorbidity and animal contact fields go...? [UPDATED]

Is this the work of the US CDC and other visitors helping the Kingdom of Saudi Arabia (KSA) Ministry of Health (MOH) resolve their Middle East respiratory syndrome coronavirus (MERS-CoV) problem? Is it an arbitrary reporting change by the Command and Control Center (CCC)? Is it someone forgetting to unhide the relevant columns in their spreadsheet?
Changes to the KSA MOH MERS-CoV public 
reporting detail after 17-March-2015.
1. The MERS-CoV graph changed scale and caught up.
2. Three fields disappeared: pre-existing disease, 
animal exposure and contact with a known cases 
within a hospital setting
3. The promise of weekly updates was dangled-
without reference to a host site.
Click on image to enlarge.

I don't know why, but since 17th March, the KSA MOH MERS-CoV reports have stopped posting information about whether each newly announced MERS case had a comorbidity and whether they had animal contact. Granted, the last field was almost always "No" or "Under Investigation" - and thus of little use (we rely almost exclusively on the World Health Organization reports to provide useful animal data) - but I wonder why the MOH has chosen to stop posting even the heading this month? 

The much more epidemiologically significant description of whether the case was an "expat" or a "Saudi" citizen remains - whew! 

And the MOH has continued to do away with all of that pesky detail that might allow an observer to link a death to a previously announced case. Thank goodness we don't have that clutter to deal with - or the details from the found113 which I presume are now completely lost in the sands of time. 

I guess the removal of these latest 2 data fields is just all part of providing the world with more of that full transparency and up-to-date information about this emerging pathogen - like the MOH "News" page - all the latest info you could want from August and earlier is to be found there. 

Oh well, at least you can get the latest from the weekly updates...if Google Translate's efforts can be understood.

It really isn't as hard as it is being made to look to get the reporting aspects right.

MERS in the UAE...

Over my weekend, the Robert Koch Institute (RKI) in Germany reported that they had a Middle East respiratory syndrome case (65 year old returning German) under their care, imported from the United Arab Emirates (UAE).[1,2]

There have been two other MERS cases hospitalized in Germany - 1 from Qatar and the other originating from the UAE, where infections are presumed to have been acquired.

This latest case is nothing astonishing but it does act as a warning that there most likely are other MERS cases circulating in the UAE. Alternatively, this person may have visited the Kingdom of Saudi Arabia (KSA) before travelling to Germany, acquiring an infection there. 

When cases emerge in other countries they can be very telling. They speak of what might be happening in the host country. The UAE has only reported (this is the important word for any outbreak observation) a single case since July last year. Was RKI just "lucky" to pick up the only other MERS-CoV case in the UAE over the past 8 months? Highly doubtful. In the absence of other information (WHO detailed data will surely follow soon), it is much more likely that MERS-CoV is circulating in the UAE, as it is in the KSA and possibly neighbouring countries, but that cases are going either undetected or unreported.


When animals were described alongside human cases.
Click on graph to enlarge.
Taken from MERS number page.
Current MERS-CoV circulation would be in keeping with the popular theory that MERS is a seasonal zoonosis (animal infection that spills over to humans causing disease on occasion), and that more primary human cases, although still relatively rare, emerge during periods when more infections are occurring in camels - which seems to occur around this time of year. That seasonality in camels has not really been established yet and still it is one popular theory among those who do not completely deny any involvement of camels in MERS whatsoever. Also worth repeating is that MERS-CoV appears to be inefficient at transmitting between people - at least so far as the testing done to date has revealed.

From the rare spillover cases acquired by humans from camels, humans proceed to do the lion's share of the work in continuing to spread MERS-CoV among humans. Yay us. 

In recent WHO disease outbreak news reports [3,4], the detailed information reveals multiple instances of cases having shared wards with laboratory-confirmed MERS-CoV cases - and despite assurances that the same healthcare workers did not attend both people, some form of contact has apparently occurred somewhere, somehow. The precise details of what that contact was, still seem to be beyond the capacity of the Saudi disease detectives to capture. But in that detail lies some important hospital (or community) transmission clues - even if those clues are as simple as revealing that the wring question are being asked, too few contacts are being tested, healthcare workers movements are not being tracked sufficiently, or finding that people (patients, contacts and healthcare workers) do not answer the question fully. 

A little thing called infection prevention and control is apparently still not being adequately adhered to in some parts of the region. 

In other words, MERS is a rare but preventable disease.

References...

  1. Flutrackers post
    https://flutrackers.com/forum/forum/novel-coronavirus-ncov-mers-2012-2014/germany-coronavirus/726247-germany-reports-3rd-imported-mers-cov-case?_=1425773133137
  2. Robert Koch Institute [German]
    http://www.rki.de/DE/Content/InfAZ/M/MERS_Coronavirus/MERS-CoV.html
  3. WHO MERS DON 06MAR
    http://www.who.int/csr/don/6-march-2015-mers-saudi-arabia/en/
  4. WHOMERS DON 23FEB
    http://www.who.int/csr/don/23-february-2015-mers-saudi-arabia/en/


A new Middle East respiratory syndrome coronavirus (MERS-CoV) table of graphs stacks up...

My new favourite graphic. 

This shows MERS-CoV detection by month since the virus was identified in 2012. Detections are further broken down by each region of the Kingdom of Saudi Arabia (KSA) in which they were reported  by the KSA Ministry of Health website here.

At the moment its highlights that the KSA has a real problem in the Eastern region (Ash Sharqiyah) and growing issue in Ar Riyad (as always with MERS-CoV detections) but that Al Quassim region is also of growing concern.

This table of graphs is part of my MERS-CoV static page to be found at... http://newsmedicalnet.blogspot.com.au/2014/08/mers-cov-daily-monthly-and-cumulative.html

I try and update these data as often as possible - at the moment detection are rising and February is currently the 4th largest month for new detections - updates occur every day or two.


References...
  1. Kingdom of Saudi Arabia Ministry of Helath MERS-CoV data http://www.moh.gov.sa/en/CCC/pressreleases/pages/default.aspx

MERS-CoV data request: A response from the Ministry of Health

Four days after I posted a blog requesting missing data on retrospective Middle East respiratory syndrome coronavirus (MERS-CoV) detections and deaths, I received a response. 

Dr Anees Sindi, Deputy Commander of the Command and Control Centrer, Ministry of Health, Saudi Arabia replied. With his permission, I have reproduced his reply below.
______________

Sent: Tuesday, 23 September 2014 6:36 PM
To: Ian M Mackay
Subject: Re: your request for missing data on retrospective MERS-CoV detections

Dear Dr. Mackay,

I�m writing in response to your blog posting entitled �A request for missing data on retrospective MERS-CoV detections.�

Thank you for acknowledging the steps that the Ministry of Health�s Command & Control Center has taken to ensure members of the public -- including researchers around the world -- have access to real-time information about MERS-CoV cases in the Kingdom of Saudi Arabia.

These daily postings are a small step on our journey toward full transparency. We want scientists to have access to the data they need to produce meaningful publications that advance our understanding of this disease for the benefit of mankind.

With that in mind, I am happy to inform you that the Ministry of Health is in the process of preparing additional data for public release. I will follow up with you once we have a confirmed release date.

Collaboration with the international research community is a key pillar of our work. In addition to sponsoring more than 30 research projects focused on MERS-CoV, the Ministry of Health has opened its doors to academics and experts from the World Health Organization and U.S. Centers for Disease Control & Prevention. MOH shares more data with the WHO than is required under the International Health Regulations, and we stand ready to support other scientists with an interest in better understanding coronavirus.

Thank you again for your interest in our work.


Best Regards,

Dr. Anees A. Sindi
Deputy Commander
Command and Control Center, Ministry of Health
Saudi Arabia


______________

This is fantastic news and I am very excited to hear that we may soon be able to complete the data picture for MERS-CoV. 

I am most grateful to Dr Sindi, the Minister and the Ministry for taking my request seriously and for replying to it so quickly.


With these data in hand, many of us will be able to build better epidemiological picture of the timing, spread and impact of MERS-CoV over the past 2 years as well as more specifically quantify MERS among fatal cases. 

These data do not answer all the questions we have of course, but they definitely answer some, and for that I'm thankful.

This social media thing does seem to have some impact.

Virus variability, dopey data and insufficient infection control do not support the theory that bioterrorism is behind the ongoing MERS-CoV outbreak.

A collaborative note from (alphabetically): @influenza_bio, @MackayIM, @maiamajumder, @neva925, @stgoldst, @kat_arden

In an unusual twist to the ever-entertaining Middle East respiratory syndrome coronavirus (MERS-CoV) narrative, a new study has been published(1,2) that calls upon us to consider seriously, or at least acknowledge, the possibility that bioterrorism explains the emergence of this virus as a rare but often deadly human pathogen. Dr Raina MacIntyre (@RainaMacIntyre) of the University of New South Wales suggests that "deliberate release" may explain the allegedly paradoxical pattern of ongoing MERS-CoV infections in Saudi Arabia. She concluded this after comparing MERS-CoV numbers to the 2003 epidemic of severe acute respiratory syndrome coronavirus (SARS-CoV).(3) Apparently, the elephant in the room that we may all be overlooking is the possibility that the virus is being or has been released deliberately in repeated acts of bioterrorism.

�Bioterrorism� is inherently an evocative and emotive word; it has the ability to elicit the sort of worry and fear among the wider community generated by the likes of �Ebola� and �deadly airborne virus�. It also feeds conspiracy theories.

In our collective opinion, bioterrorism, with respect to MERS-CoV and otherwise, should not be invoked without at least some preliminary data that point specifically to a deliberate human cause. 

We would like to make it clear that we don't object to considering bioterrorism as a potential cause of the emergence of MERS-CoV. It is always worth considering whether an outbreak of any human, animal or plant disease is due to deliberate human activity. Thankfully, there are people whose jobs are to do just that. 

However, we have some concerns about the rationale put forth in Dr. MacIntyre's paper regarding why bioterrorism may explain sporadic MERS-CoV infections better than nature and would like to highlight some notable factual errors and omissions that might have influenced her conclusions. No data are available that could decisively rule out the possibility of bioterrorism as the cause of the ongoing MERS-CoV outbreak, as one cannot prove a negative. Nonetheless, we believe that Dr. MacIntyre's arguments are flawed and that the available evidence cannot be used to support her theory. Substantial scientific and methodological problems exist in Dr MacIntyre�s paper that undermine her deliberate release theory. Here, we discuss some of these issues, and we offer perspective on why bioterrorism is unlikely to be a cause of human or animal MERS-CoV infections.

MERS is different to SARS. Yep. We already knew that.

A substantial amount of Dr MacIntyre�s report is based on comparing MERS to SARS.(4) MERS-CoV and SARS-CoV are genetically, taxonomically and phylogenetically divergent, and MERS and SARS are immunobiologically, clinically and pathologically distinct. Furthermore, their transmissibility in humans, their environmental contexts, their animal hosts and the interactions between their animal hosts and humans are different. Thus, the comparison between the two viruses must, a priori, result in finding MERS and SARS outbreaks to be characteristically different. That SARS and MERS are different has also been stated previously.(5,6) Compared to SARS, MERS generally progresses more rapidly and occurs more frequently in individuals with pre-existing medical conditions, including diabetes, chronic lung disease, renal failure and in people who are immunocompromised. Moreover, MERS-CoV exhibits a broader tissue tropism and induces faster cellular damage than SARS-CoV; it also employs a completely different receptor and prompts a comparatively delayed cellular immune response. These two viruses belong to separate lineages within the genus Betacoronavirus; they are chalk and cheese.

Moreover, from an epidemiological viewpoint, it is extremely important to note that human cases of infection with these two viruses have never geographically overlapped. This is no small fact. The population of Saudi Arabia seems to have an unusually high proportion of older males (Fig 1) with pre-existing medical conditions; from the data that are currently available, this particular group also appears to be most vulnerable to fatal outcomes. Outside this population, MERS-CoV infections seem to be far less frequently associated with severe disease and death.
 
Figure 1. Older males represent a greater proportion of MERS cases and even more of the deaths attributed to infection with MERS-CoV.

Perhaps most salient to this discussion is that MERS-CoV does not transmit in humans as well as SARS-CoV did. In fact, MERS-CoV transmits quite poorly between humans unless a perfect storm of pre-existing medical conditions and poor infection prevention and control in a healthcare setting, and perhaps the right environmental factors, occur. 
Dr. MacIntyre compared epidemic curves for SARS and MERS to show that, aside from this year�s March/April hospital outbreaks, the appearance of new MERS cases doesn't follow the same pattern that new SARS cases did. Namely, new MERS cases have continued to appear at a trickle, up until a few weeks ago, whereas SARS disappeared entirely once human-to-human transmission was stopped. One explanation for this is that the Arabian Peninsula has a lot more domesticated camels, which are believed to be the primary host reservoir for MERS-C0V, than China has captive civet cats, which serve as an intermediate host transmitting SARS-CoV from bats to humans. For this and other reasons, there may be a far greater number of opportunities for repeated zoonotic transmission of MERS-CoV than there was for SARS-CoV. In support of this idea, it has been found that those who work with camels are at greater risk of acquiring MERS-CoV than are those who do not.(7) 

In short, MERS-CoV is barely contagious among humans but highly zoonotic, and SARS is highly contagious among humans but barely zoonotic.

All of these considerations are reasons to dissuade one from expecting much overlap between the epidemiology of SARS and that of MERS.   

Dr. MacIntyre's arguments that some features of the MERS outbreak may be specific to the repeated, deliberate release of MERS-CoV are not supported by evidence.

Dr. MacIntyre states that the ongoing MERS outbreak appears to involve "sporadic ongoing infections from a non-human source." We agree, with the caveat that such infections represent a minority of cases; most cases have resulted from short human-to-human transmission chains in healthcare settings.8 Dr. MacIntyre further states that, "Possible sources of ongoing sporadic infection in humans include animals (camels appear the most likely source), or deliberate release." However, she argues that the epidemiological data may be more easily explained by deliberate release than by infections acquired from animal (camel) sources.

The main features of MERS-CoV infections that are suggested in Table 1 of Dr. MacIntyre's paper to distinguish between deliberate and natural infections are the following:

   In support of deliberate release, but not natural infections:
  1. "Evidence of multiple introductions in a single outbreak."
  2. Possibly, "Several cases with no link to human OR zoonotic source."
  3. Possibly, "Multiple genetic strains in a single hospital outbreak at Al Ahsa Hospital."
   In support of natural infections, but not deliberate release:
  1. "MERS-CoV identified in camels."
Below, we respond to each of the features of the ongoing MERS-CoV outbreak that Dr. MacIntyre has suggested provide evidence in favor of deliberate release.

  1. MERS is repeatedly introduced into the human population, most likely because humans are repeatedly exposed to animal sources of the virus.
    While we have yet to see seroprevalence data (though we have on good authority that community seroprevalence is low and a detailed report on the matter will be released soon), no evidence of high population prevalence exists. So far, cases have been sporadic without prolonged chains of human-to-human transmission. Healthcare settings, especially hospitals, have served as both amplifier and nexus for human-to-human spread; approximately 75% of the surge of cases in Saudi Arabia during March-May 2014 are thought to have resulted from human-to-human transmission, primarily in these settings.(9) In fact, many cases initially thought to have been primary, zoonotic cases have subsequently been linked to exposures to confirmed human cases.(8) Also, more than 25% of all cases have been healthcare workers, highlighting the extent of nosocomial (hospital-related) transmission.(8) Moreover, despite Dr MacIntyre�s assertions, a substantial proportion of cases have been mild. Between a quarter (of detections worldwide) and a third (of 113 previously unreported cases announced by the KSA Ministry of Health in early June 2014) were asymptomatic, i.e., they had no notable signs or symptoms of illness.

    However, until a pause this July, new MERS cases have been detected almost continuously at low levels over the past year or more. Aside from outbreaks in healthcare settings, these cases are thought to be by and large primary, zoonotic cases, i.e., caught from an animal source, most likely related to camels. Thus, we agree with Dr. MacIntyre that many MERS cases are likely due to multiple introductions into humans; however, we disagree with the idea that this points more to bioterrorism than to an animal source. Instead, we believe that multiple introductions into humans more likely reflect ongoing exposures to infected animals or contaminated animal products; a lot of camels live in and are also imported into the Arabian Peninsula. It is important to note that multiple introductions into humans have also been observed with other zoonotic pathogens as well, including highly pathogenic avian influenza A (H5N1) virus(10) and avian influenza A (H7N9) virus.(11) Existing health conditions have an impact on disease outcomes in such other zoonotic diseases, too. Repeated introductions of a virus into a human population are not unique to bioterrorism; nature does a very good job of creating confounding epidemiological conundrums that are often made worse by inadequate human responses.
  2. We don't know of a source of exposure for a proportion of MERS cases, but that's probably just because we don't have perfect information.
    Small numbers of sporadic cases have been reported for which no contact with other confirmed cases or animals is known. Dr. MacIntyre suggests that the simplest explanation for these cases may be bioterrorism. In our opinion, however, these cases may be explained most simply by the pervasiveness of incomplete case histories, and occasionally by contact with undiagnosed cases, rather than by the deliberate release, past or ongoing, of pathogens into the environment. Moreover, patients or their relatives may not be aware of all relevant interactions with animals or animal products, and we also may not be asking the right questions about those interactions. We will simply never know about all relevant contacts for every infected person; we never really do for any viral outbreak. MERS is a fairly new disease, and even the experts are unclear about how MERS-CoV is transmitted from camels to humans or even from humans to humans, for that matter. Let's figure out the basics before we say that bioterrorism is a more likely cause than nature.
  3. Genetic variability among different human MERS-CoV variants is small and probably results from natural variability in MERS-CoV; viruses are naturally diverse.
    The fact that multiple MERS-CoV strains were detected in a single outbreak at Al-Ahsa Hospital suggests only that the outbreak resulted from human-to-human transmission of virus introduced via multiple zoonotic events that exhibited some expected genetic variability. Such multiple introductions have been documented and explained already.(12) While it�s possible (though unlikely) that several viral variants were deliberately released, nature is quite capable of doing this without human help.

    Genetic variation among MERS-CoV isolates has indeed been detected in Saudi Arabia. However, the changes have affected <2% of the entire genome, a degree of variation that is not uncommon within other endemic human coronaviruses. Virus variation can also occur among MERS-CoV strains passaged through cells in culture, indicating that virus-driven adaptive changes are not unusual in this virus under a variety of host and growth conditions. Furthermore, the genotypes found in both camels and humans throughout the Arabian Peninsula have generally been no more or less divergent than what we�ve seen in Saudi Arabia thus far. The exception is a strain found in a camel in Egypt that had been imported from Sudan or Ethiopia;(13) this strain is notably more divergent and may hint at an as yet untapped source of variation to be found in geographically dispersed cousins of the Saudi viruses.  Genetic variability occurs naturally among viruses, including zoonotic viruses,(14) and is not a hallmark of bioterrorism.
There are better ways to explain the unusual features of the observed epidemiology of MERS-CoV.

Dr. MacIntyre states, "The continued increase in cases in KSA in 2014, without satellite epidemics in other countries, and without consistent animal contact in all cases is inexplicable." These observations are not inexplicable for a virus that transmits poorly. We argue that satellite epidemics have not been observed simply because secondary, human-to-human spread of MERS-CoV is rare and is, moreover, most likely attributable to a small percentage of cases. We have seen evidence for such inefficient transmission in almost every exported MERS case to date. People sitting next to a confirmed case during tours and on planes have not become ill; nor have they tested positive for MERS-CoV. Apart from weaknesses in the virus and environmental factors (e.g. temperature, humidity, outside camel birthing season), good infection prevention and control may also play a role in limiting spread. 

Dr MacIntyre suggests, further, that, �If the large recent increase in cases in KSA is due largely to person-to-person transmission, other similar increases (satellite epidemics) would be expected in other countries.� However, even though satellite epidemics have not occurred, it is a fact that most cases in the spring in the KSA were due to human-to-human transmission. The healthcare-related outbreak in Jeddah was tied to location-specific failures of infection prevention and control, as the World Health Organization (WHO) has pointed out.(8,15)

As for cases "without consistent animal contact," we hope that Dr. MacIntyre is not expecting proof of animal contact for every case, but rather for suspected primary cases only. As discussed above, most cases have reportedly resulted from human-to-human transmission, and the rest are probably accounted for by incomplete medical case histories and overlooked contacts with an undiagnosed case or infected camel source. Alas, for some primary cases, we simply do not have enough information yet.

The epidemiological data used by Dr MacIntyre, courtesy of the Saudi Arabian Ministry of Health and the WHO, are imperfect. Those of us maintaining MERS-CoV detection line listings are painfully aware of the limitations associated with these data and their communication. Reporting formats have changed repeatedly, resulting in inconsistent case histories. Testing delays, reporting gaps, incomplete case information and translation errors are but a handful of issues that must be considered and controlled for when using these data to improve our understanding of MERS epidemiology.

Yes, there have been seemingly incongruous pauses in case announcements during periods of mass gatherings � times when we might expect detections of a respiratory virus to be on the rise. Yes, it appears, from the data alone, that only a handful of cases have reported animal contact, despite the fact that about 25% of human cases have been zoonotic, according to the WHO.(9) Yes, countries with cases outside Saudi Arabia more often report contact with camels. However, these �paradoxes and inconsistencies� are far more likely due to incomplete and inconsistent data collection and reporting than to a �deliberate release� of MERS-CoV as a putative category C bioterrorism agent.

How likely is it that MERS-CoV is a cultured pathogen deliberately released by bioterrorists?

The likelihood that MERS-CoV was deliberately released in Saudi Arabia is vanishingly small, and Dr MacIntyre�s article fails to provide any sound scientific basis to convince us otherwise. Each of the features of the ongoing MERS-CoV outbreak that she has put forth as an indicator of deliberate release can also occur naturally. In addition to the issues discussed above, Dr MacIntyre offered no explanation to describe a mechanism by which MERS-CoV could have been weaponized; however, given what we do know about MERS-CoV, purposeful weaponization seems highly improbable. Thus, while it is worth considering whether any disease outbreak has a deliberate human cause, Dr. MacIntyre's paper provides no evidence that supports bioterrorism as a cause of MERS. Instead, an abundance of evidence suggests that MERS results from natural causes.

MERS-CoV is known to infect dromedary camels across the Arabian Peninsula and Africa; we likely know of only a fraction of its geographic range in the latter. Moreover, the virus has been in these animals for at least 20 years. As we continue to learn, it�s looking more and more like an ancestor of MERS-CoV first emerged in bats, potentially in Africa.(16,17) If the virus did spill over from bats to camels at some point, it remains unknown when or how, as does the scope of how many other animals carry some version of MERS-CoV-like viruses. 

So, does any of this mean that a deliberately engineered form of the bat virus was purposefully released into camels more than two decades ago? Could it have been a (very poorly functioning) bioweapon intended for use against camels? Who would have created such a weapon? Or, was such a virus potentially introduced into humans first and we�ve been the source of camel infections ever since? Due to the large genome sizes of coronaviruses (the largest among all RNA viruses), reverse genetics systems, used for �made-to-order virus� construction, are quite cumbersome and demanding; only a handful of labs are known to be proficient with these systems. These significant technical requirements provide further evidence against the possibility that MERS-CoV has been used as a bioweapon.

Dr. MacIntyre states that, �when a new infectious disease emerges, bioterrorism, unless it is caused by an eradicated disease such as smallpox, may not be easily recognized for what it is unless we consider the possibility.� This, however, is not supported by the last decade of research and development, undertaken across the world, towards the goal of preventing, detecting, and mitigating the effects of bioterror. Since 2001, considerable resources have been invested in preparing for bioterrorism. This has led to the deliberate and explicit �securitization� of public health and medicine, with a focus on conceiving the potential for human-caused disease outbreaks.(18) The focus on man-made viruses and the potential for bioterror is a multibillion dollar enterprise;(19) if the status of MERS-CoV as an intentional release  agent were plausible, it would provide rare vindication for such efforts. That it has not is not for want of attention on the behalf of policymakers around the globe.

It is also worthwhile to reflect on the reasons one might release a pathogen and how the ultimate goals of any purported bioterrorist might inform their release strategy. The two iconic instances of bioterror�separate from biological warfare�in the twentieth century were the use of Salmonella enterica by the Bagwan Shree Rajneesh cult in Oregon in 1984 and the 2001 anthrax attacks.20 In both, a bacterium was used with very specific goals: the attempted manipulation of a local election and the targeting of US public service institutions. 

A poorly transmitting coronavirus, however, could not be targeted as well as the pathogens used in the above cases. It isn�t an ideal agent for more common attempts to use pathogens as weapons, either, such as the failed attempts to weaponize anthrax and the botulinum toxin by the Aum Shinrikyo doomsday cult.(20) Rather, MERS-CoV occupies a biological limbo in which its effects are too intermittent for it to be a targeted agent, but nowhere near prolific enough to be a means of generating widespread bioterror. If MERS-CoV were to be�counterfactually�a bioterror agent, then its creators would have surely failed at their task. 

We don�t see too many new diseases; there are only so many ways a pathogen can make us sick. In this sense, MERS is not really clinically distinct, and certainly nothing about MERS can be pointed out as pathognomonic; however, there still remains much to learn about the epidemiology, clinical course and virology of the disease. This is quite commonly the case, even two years after the discovery of a new viral species. By all means, investigators should consider all potential causes of outbreaks of new human pathogens, even bioterrorism. However, in the case of MERS, while detailed laboratory, epidemiological and clinical studies are absent or found wanting, the publicly available data that exist are consistent with a natural origin for the outbreak. The simplest explanations are likely still the best; in this case, when we hear hoof beats, we shout camel, not bioterrorist.

References.
  1. MacIntyre, C.R. The discrepant epidemiology of Middle East respiratory syndrome coronavirus (MERS-CoV).
    http://link.springer.com/article/10.1007/s10669-014-9506-5/fulltext.html
  2. https://storify.com/MackayIM/evoking-bioterrorism-as-a-cause-of-sporadic-mers-i/edit 
  3. http://www.who.int/ith/diseases/sars/en/ 
  4. SARS and MERS are the diseases associated with SARS-CoV and MERS-CoV infections, respectively.
  5. http://www.cdc.gov/coronavirus/mers/faq.html
  6. http://www.who.int/csr/disease/coronavirus_infections/MERS_CoV_RA_20140613.pdf?ua=1
  7. http://www.who.int/csr/disease/coronavirus_infections/MERS-CoV_summary_update_20140611.pdf?ua=1
  8. http://www.who.int/csr/disease/coronavirus_infections/MERS_CoV_RA_20140424.pdf?ua=1 
  9. http://www.reuters.com/article/2014/05/14/health-mers-meeting-idUSL6N0O03TQ20140514
  10. http://www.who.int/influenza/human_animal_interface/H5N1_cumulative_table_archives/en/
  11. http://www.who.int/influenza/human_animal_interface/influenza_h7n9/Data_Reports/en/
  12. http://www.ncbi.nlm.nih.gov/pmc/articles/PMC3898949/
  13. http://wwwnc.cdc.gov/eid/article/20/6/14-0299_article
  14. http://www.ncbi.nlm.nih.gov/pubmed/24457975
  15. http://www.ncbi.nlm.nih.gov/pubmed/23891403
  16. Corman VM, Ithete NL, Richards LR, Schoeman MC, Preiser W, Drosten C, Drexler, JF. Rooting the phylogenetic tree of MERS-CoV by characterization of a conspecific virus from an African bat. J Virol. 2014 Jul 16. http://jvi.asm.org/content/early/2014/07/10/JVI.01498-14.abstract
  17. Yang L, Wu Z, Ren X, Yang F, Zhang J, He G, et al. MERS�related betacoronavirus in Vespertilio superans bats, China [letter]. Emerg Infect Dis. 2014 July. http://wwwnc.cdc.gov/eid/article/20/7/14-0318_article
  18. Fidler, David P, and Lawrence Ogalthorpe Gostin. 2008. Biosecurity in the Global Age. Stanford University Press. 
  19. Elbe, Stefan, Anne Roemer-Mahler, and Christopher Long. 2014. �Social Science & Medicine.� Social Science & Medicine, May. Elsevier Ltd, 1�9. doi:10.1016/j.socscimed.2014.04.035.
  20. Wheelis, Mark, and Lajos R�zsa. 2009. Deadly Cultures. Harvard University Press.

Where has all the MERS-CoV action been...?

Sorry but no prizes to be awarded here.

...the Kingdom of Saudi Arabia is where nearly 90% of all laboratory-confirmed detections of the Middle East respiratory syndrome coronavirus (MERS-CoV) have originated from, as best we can tell. 

This is based on data sourced from the World Health Organization, various Ministries of Health around the world, FluTrackers and the scientific literature. All public data sources. 

While the tally sits around 847 cases and 291 deaths, right now we are experiencing a multi-week lull in new case announcements. Great news for the region and the world, which is dealing with many assaults, biological and otherwise, right now.

Where the wild MERS-CoVs are.
Click on chart to enlarge.

MERS-CoV in June/July...

Looks like MERS-CoV cases, while few in number, remain well distributed across nearly all of the Kingdom of Saudi Arabia still.

With such a remarkably widespread distribution one must ask, where are these cases coming from? In the absence of any noted hospital outbreaks, do we assume that they are all from animal>>human acquisition?

And what is it about Ha'il, Jizan and Qasim provinces that are protecting them during this period?

Middle East respiratory syndrome coronavirus activity in June and July in the Kingdom of Saudi Arabia. The pale orange regions have had cases noted, Only Ha'il, Jizan and Qasim provinces have not yielded any MERS-CoV detections.
Click on map to enlarge.

Jeddah changed the MERS-CoV age:sex landscape...

Note. Not every death or case is listed.
See bottom-left corner for breakdown.
Click on charts to enlarge.
I've broken down the age and sex in these charts.

As usual, it's mostly about males and older people until we get to the Jeddah outbreak.

In the top pair of charts (note the different scale used here compared to that used in the charts below) we see the breakdown for all MERS-CoV detections to date on the left and the fatal cases from among those on the right. 
An apple in terms of people shapes.

In the middle pair of charts we look at all cases form 2012 up until the day before the Jeddah outbreak. The total case pyramid shows an older age bulge but the deaths look very similar to those for all fatal outcomes. M:F is similar to the total case charts above.

In the bottom pair of charts we're looking at what happened from the beginning of the Jeddah outbreak until now. We see a marked change in distribution with many more younger adults being positive for MERS-CoV. We also see a major shift towards more females than we'd seen beforehand. All the result of more widespread testing and a greater healthcare worker contribution I presume. Strangely though, given the younger adult demographic here, we see no accompanying jump in numbers of children. Are they not subject to testing? Are the younger adults often foreign workers who do not have children/children with them with them? There is no reason for children to test any less frequently MERS-CoV-positive and they are also just as likely as healthy adults to get mild or asymptomatic disease (as far as we know). If positive, children will have an important potential role in the MERS-CoV transmission story, especially when visiting elderly relatives.

The recent Al Qunfudhah teacher who is MERS-CoV just reinforces that children are shaping up to be a strange data gap. Yeah. I know. Another one.


MERS-CoV cluster in Al Qunfudhah...

5 cases in 4 days from a city we haven't seen prior MERS-CoV detection in (as far as I can tell) = a cluster.

The south western coastal city of the Kingdom of Saudi Arabia (KSA) is home to ~200,000 people[1].

While the cases have been asymptomatic when reported, the first, a 65-year old male (65M; was isolated at home [2]), came into contact with another case (see below) while at a government hospital. Which case that was and at what hospital, is unclear.

But there are other worrying issues here:
  • This city is in Makkah region, home to the 2 holiest Mosques and not a site in which anyone wants to see active spread of this virus again as we get closer to the Hajj; we don't want to see it spread anywhere at all of course.
  • FluTrackers has a thread on this (when don't they!?; my thanks to Sharon Sanders for pointing me to it) from 21-May and at least one of the 5 cases seems to be a teacher at a school in Al Quoz, 25 km south of Al Qunfudhah. No school-children have been reported positive to date though. The 4 cases after 65M were aged 25, 28, 25 and 45 - could some be teachers or are they all family of 65M? Family accompanied 65M to visit a relative in a Jeddah hospital (presumably the contact for 65M?). We no longer get any information from the KSA's Ministry of Health (MOH) about occupation, so one is left to guess...as usual. There seems to be mention of symptoms among some of these cases?
  • Could healthcare workers in Al Qunfudhah be among these younger asymptomatic (presumable) contacts of 65M?
This city may be seen written as Al Qunfudah, Qunfudah, Qunfutha, Kunfuda, Gonfodah or Gonfothah. I was helped out on the naming of this city recently - my thanks to @AmboceptorBlog


Sources...
  1. http://en.wikipedia.org/wiki/Al_Qunfudhah
  2. http://www.moh.gov.sa/en/CoronaNew/PressReleases/Pages/mediastatement-2014-05-22-001.aspx
  3. http://www.moh.gov.sa/en/CoronaNew/PressReleases/Pages/mediastatement-2014-05-24-001.aspx
  4. http://www.moh.gov.sa/en/CoronaNew/PressReleases/Pages/mediastatement-2014-05-25-001.aspx
  5. http://www.flutrackers.com/forum/showthread.php?p=535788#post535788

Snapdate: MERS-CoV detection by month...

We are living in the 2.17th year, or 113th week, since the first known MERS-CoV-related illness affected a 25-year old Jordanian.

April stands out as the biggest MERS-CoV detection month ever, with 286 cases either becoming ill, being hospitalised or being reported as positive. But don't be confused by the differing values on the axes in the chart below. For all that May looks like a smaller cousin of April, its tally has already outstripped every other month of 2012 or 2013. 

72 cases so fall into May. But the rate of cases this month is slower than in April (see previous post). 

The tally of detections announced officially through WHO (which remains in a galaxy far, far, far away when it comes to detail on April-May cases) and from various Ministries of Health brings my worldwide tally to 580 MERS-CoV detections listed of which ~166 people have died of MERS. I'm still awaiting detail from WHO or UAE on 4 MERS-CoV cases that I do not list.

38% of May's case have died compared to 13% of April's (where I'm able to assign fatal cases to a month).

Click on image to enlarge.

VDU Quote for the night...

From:
Z.A. Memish et al. 
Screening for Middle East respiratory syndrome coronavirus infection in hospital patients and their healthcare worker and family contacts: a prospective descriptive study.
Clinical Microbiology and Infection, 2014.
"Surveillance studies also help in defining and monitoring transmission rates, case load, and epidemic risk assessment, and assist in instituting infection control measures with new diagnostic methods and treatments."

Snapdate: MERS-CoV detections near 500...

MERS-CoV detection by day; Jeddah outbreak.
Click on image to enlarge.
Welcome to the beginning of MERS-CoV's 112th week (2.15 years). We sit at 497 cases (probably over 500 if the United Arab Emirates would confirm their cases with some extra data that made them more identifiable and "real". For now, I'm not including them after the recent issue around theUAE12. For now my count says at 497 with ~131 deaths (26.3%).

Judging by tonight's announcement of only 3 cases (only 1 with an onset date which was 24-Apr), let's hope this is the week where the Jeddah outbreak gets put to bed.

MERS-CoV detection by week 2012-present.
Click on image to enlarge.
Also, make this the week that the Kingdom of Saudi Arabia's(KSA) Ministry of Health adds some consistency to its releases. They've been doing a 100% improved job in the past weeks, adding much more detail, but it needs to be the same detail for every case, every day. And the listing of deaths and recovered cases is also great; but is currently not able to be linked to the original announcements so we don't know where they these people were from, comorbidities, HCWs etc as there are often 2 or more people from the same region with the same age. A date of affliction is needed to permit the linkage between original announcement and death/recovery. Just 1 more variable guys. Pleeease.

Nonetheless the dailies seem to be slowing, although the cumulative average still strolls upwards but in a linear, not exponential manner.

We stay tuned.


MERS-CoV by month, now with added camels and hospital outbreaks...

Weekly case tallies for 20012-4 (blue-surviving 
and fatal cases; red-fatal cases). Also indicated 
are the season in which camels give birth (I've
noted "birthdays" because it seems to be 1-year

old or older camels that are usually positive for
MERS-CoV. Past and future Hajj pilgrimage 

dates are also shown as is 1 of several
large camel events in the KSA.
Click on image to enlarge.
While the World Health Organization is yet to produce confirmed case data for the majority of the MERS-CoV outbreaks' biggest month, some of those data and extra information are being provided by the Kingdom of Saudi Arabia Ministry of Health v2.0. 

And it's very welcome and much appreciated. There still remain some vagaries and data gaps that make consistency an issue. But further information is not forthcoming so let look at some charts of what we have. 

For now, we can see in the daily graph, 4-days into May, that cases are still being announced but at what looks like a slower rate. We are seeing cases reported with a lag of approximately a week from when they became ill/were hospitalised (when those dates are present).

A plot of cases per day. Many (?most) are based on dates of reporting although
more dates of illness onset have emerged lately and I am working through them. This means that the specific peaks may chop and change a little as dates are assigned. Nonetheless, the trend seems to be one of decreasing numbers per day and
the cumulative average may be suggesting a peaked for this KSA outbreak.
Click on image to enlarge.

MERS in the USA....

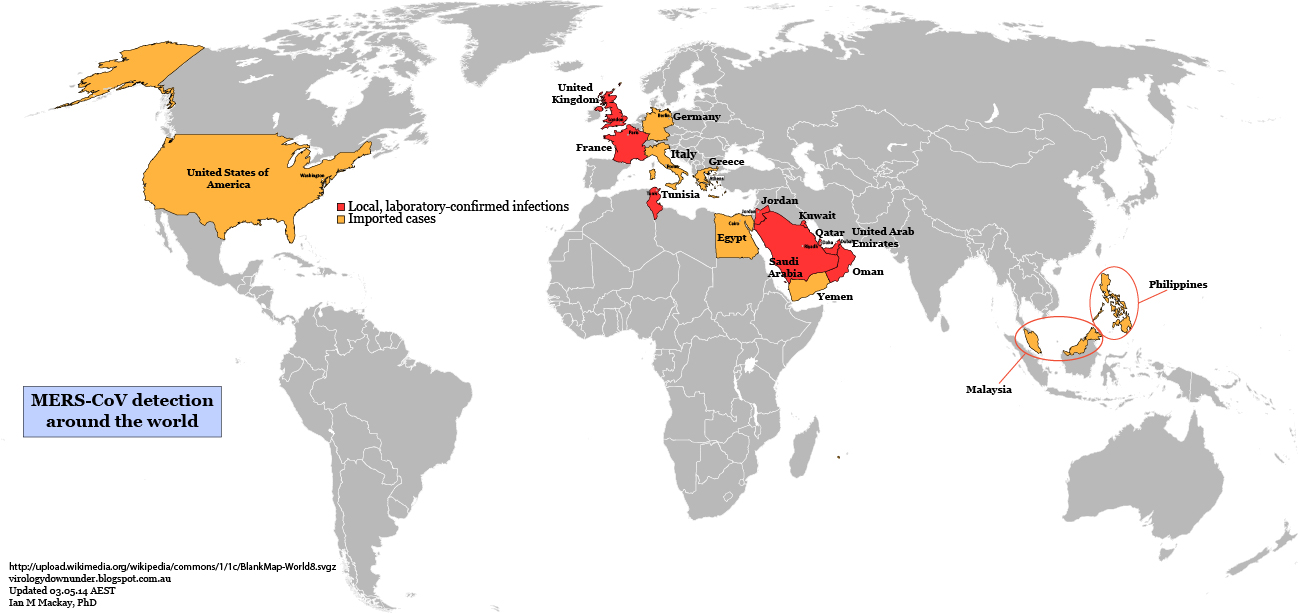
The source of all exported MERS-CoV positive people lies within the Arabian peninsula. Very limited local spread has occurred within 3 non-peninsula countries.
Click on image to enlarge.

The Middle East respiratory syndrome coronavirus (MERS-CoV) made its way to another country yesterday; the United States of America (USA).


MERS-CoV in the KSA during April.
Filled red circles mark towns and cities for general interest.
The darker sandy coloured areas indicate KSA Regions
(also Egypt and the United Arab EMirates) where
MERS-CoV detections have been located recently.
Click on image to enlarge.
This is not a big surprise and it's not the end of days, but dude...it lit up Twitter and had reporters high-five'ing like nothing the 460 cases before it, mostly around the Arabian peninsula, managed to achieve. But then MERS-CoV detections have only been accruing for 111 weeks. 

These things can take time to warm up.

The USA case was in a healthcare worker (HCW) travelling back from the Kingdom of Saudi Arabia (KSA).

What else do we know?

  • FluTrackers #456
  • The HCW who was working in Riyadh, KSA, travelled back from there to Chicago in the USA via a transfer at Heathrow airport in the United Kingdom, 24-Apr.
  • Illness became more noticeable 27-Apr (coughing, shortness of breath and fever), and the person was hospitalized 28-Apr in Indiana.
    Was less noticeable illness present first? We know little about what the earliest inklings that someone has a MERS-CoV passenger feel/look/sound like.
  • Age and sex of the patient have not been officially released.
    I should stop complaining about that from the KSA Ministry of Health data. Still important to know it, but if its not provided by one high income economy, why expect it to be provided by any other?
  • The laboratory confirmation was made 2-May (~4-days)
Because the person wasn't coughing, sneezing or noticeably wheezing on the planes, it will be unlikely that any virus was propelled towards, or impacted upon surfaces shared by, people nearby. We will of course be watching as the USA health professionals track, observe and hopefully swab and test at least some of the contacts from the planes and post-transit spaces. These people can tell us a lot about what the virus is doing among people not defined as "close" contacts; a kind of live experiment to check if MERS-CoV transmits any differently now than it did the last time it got loose from the Arabian peninsula. On those recent occasions neither Greece, Malaysia nor the Philippines saw any additions to the transmission chain.

I can remember when MERS and H7N9 cases were so rare I used to do a work up like this on each announcement. Ahh the good old (slow) days.

Sources...

  1. http://www.cdc.gov/media/releases/2014/p0502-US-MERS.html
  2. http://www.in.gov/activecalendar/EventList.aspx?fromdate=5/1/2014&todate=5/31/2014&display=Month&type=public&eventidn=169819&view=EventDetails&information_id=200566&print=print

Like Us

Blog Archive