Medical News Blog Information

Showing posts with label avian influenza. Show all posts

The third outbreak of influenza A(H7N9) virus seems to be over...

Cumulative curves of reported H7N9 cases and deaths in humans.
Click on graph to enlarge.
By the looks of the curve on the right, the rush of cases that defined the third known outbreak of the low pathogenicity avian influenza A virus subtype, H7N9, is over...for another season anyway. 

If we get into the nitty gritty, as I have below, there are a couple of interesting things to see. First though - let us remember that these are just reported data:

  • there may have been some cases that were not reported for whatever political, medical, social or personal reasons - these data are an idea of what happened - look at the rends and don't get hung up on the specific values
  • the overwhelming majority of the cases have reported to a healthcare facility with respiratory disease due (presumably) to either infection - we have no idea how many other people have been infected, what proportion were mild or asymptomatic (as I've discussed e.g. here and here, so we know it is possible). It could be half as many again, or 100 or 1,000 times as many.
  • these are only cases that have been examined with a laboratory test (as far as we know) - there may have been many other cases of "influenza-like illness" that did not get sampled and tested but were managed under (or not) the assumption that they were influenza of some type, subtype or strain.

Please note-the graphs used here can all be found on my fixed interactive H7N9 page at:http://newsmedicalnet.blogspot.com.au/2014/11/influenza-ah7n9-virus-detection-numbers.html

The interesting stuff includes:

  • For the 2 outbreaks we have continuous data for - 2013-14 and 2014-15, the start of the outbreak seems to be around October/November, with the peak around January/February. 
  • Outbreak 3 did not seem to reach the heights of the preceding year however, from what we could glean from pretty poor data, the link to poultry exposure was as strong as ever. Perhaps market closures in response to deaths were a little more effective/efficient/wide-ranging in Outbreak #3? Pure speculation

Click on graphs to enlarge.
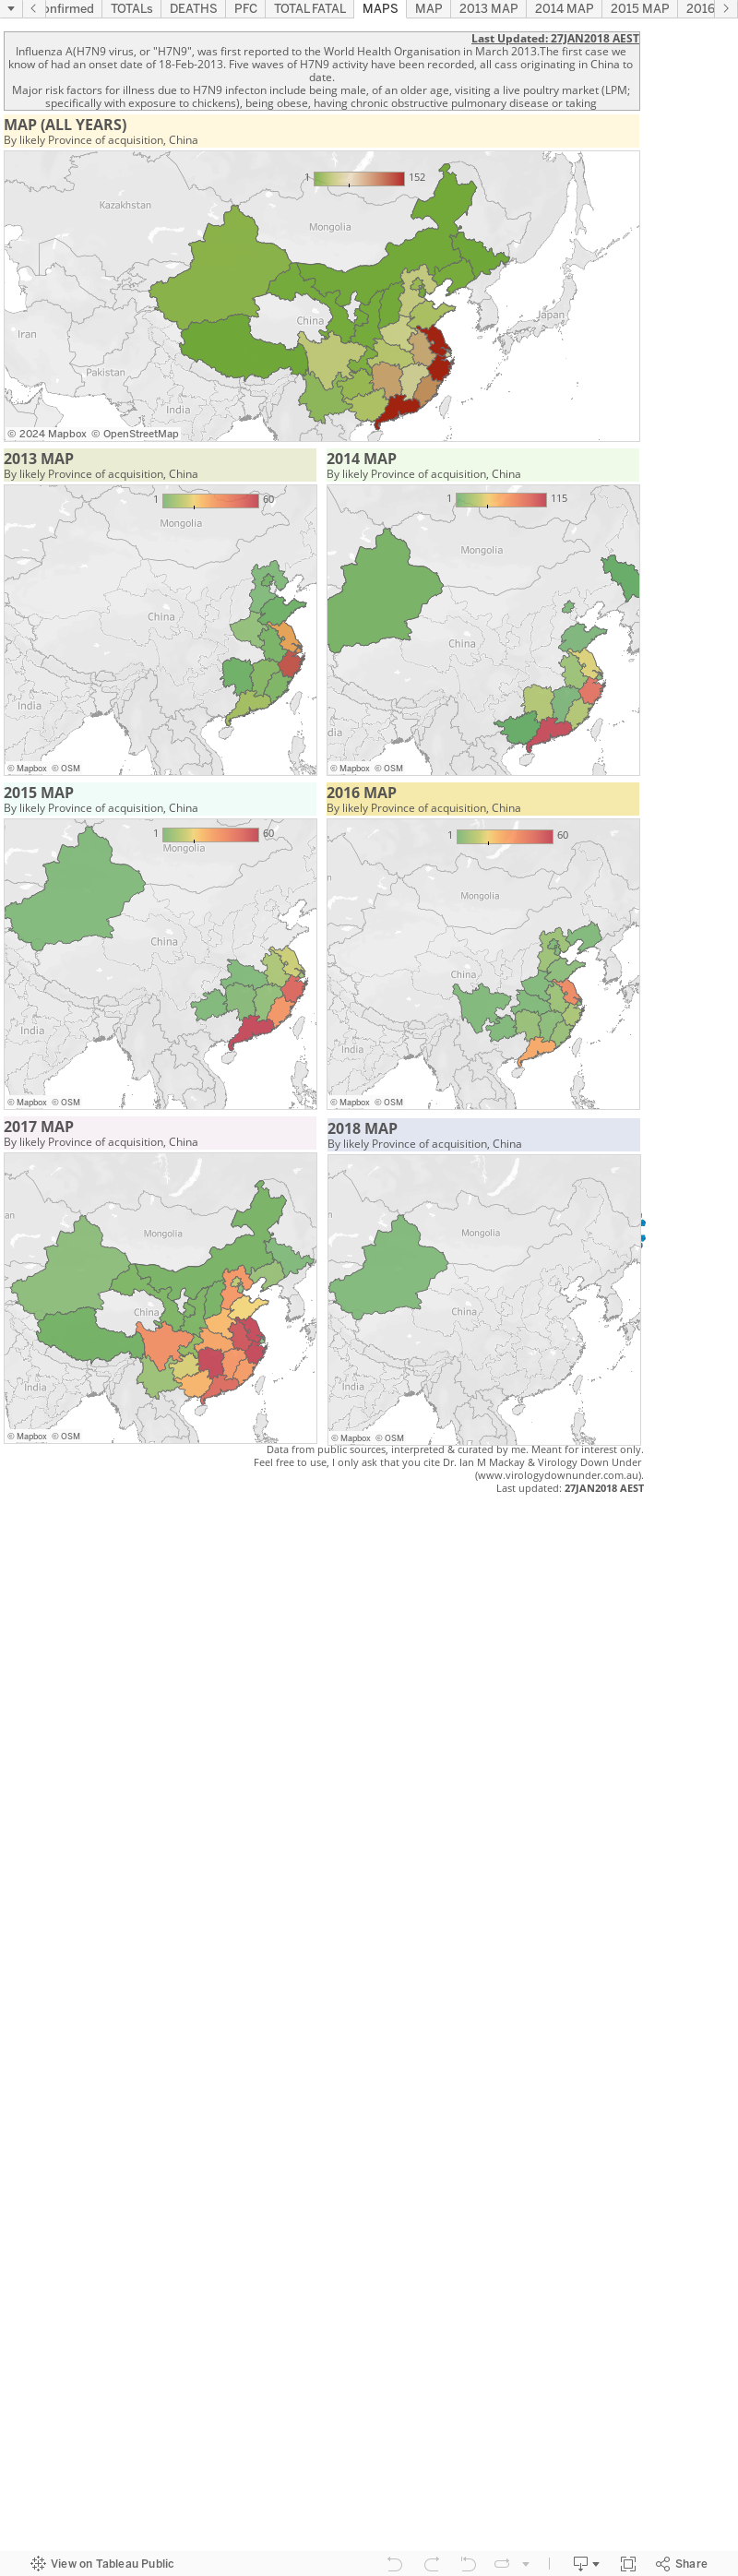
  • Most of the cases in 2015 (bottom maps) were on the east coast of China

Click on map to enlarge
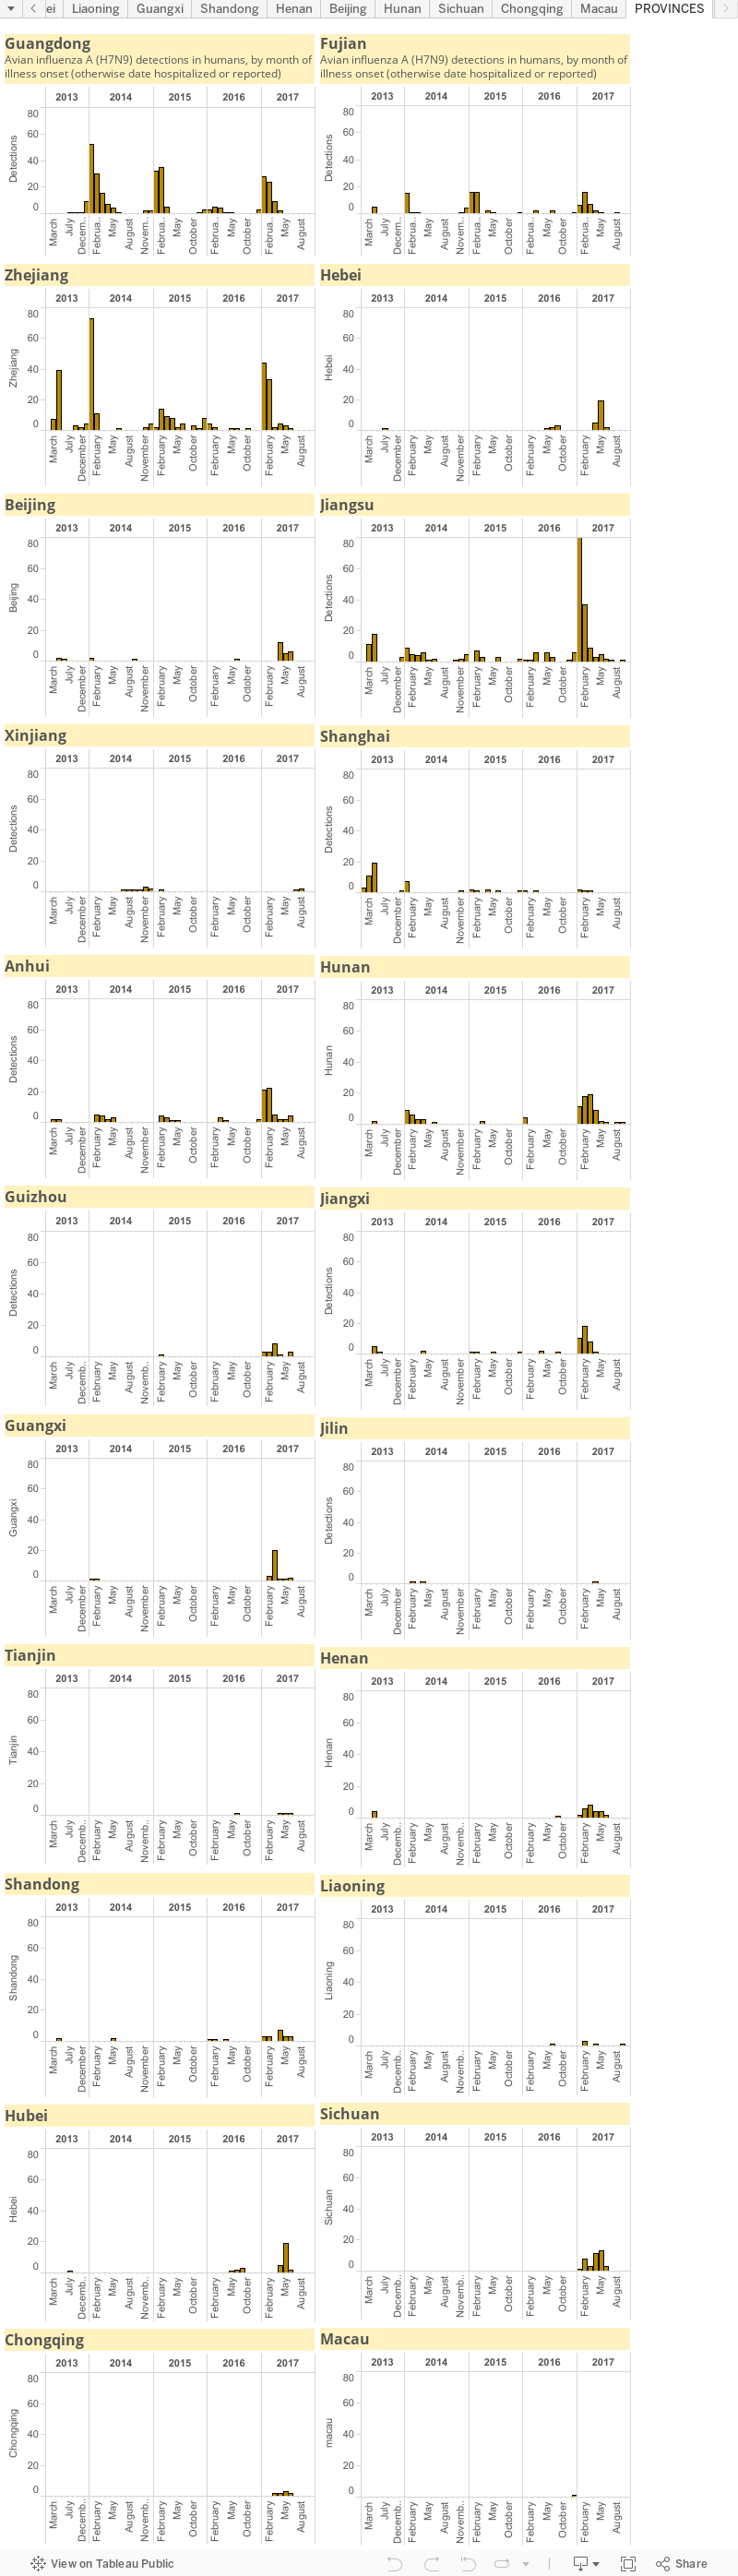
  • Most of the activity in the 3rd outbreak was focussed in Guangdong, Fujian and Zhejiang provinces (the red ones above) 
  • Xinjiang Uyghur Autonomous region (in the far west) and Guizhou and Hubei provinces joined the list of host regions in Outbreak #3
  • Xinjiang joined Guangxi and Jilin provinces (which reporting cases in Outbreak #2) as regions of China that share a border with another country - heralding the movement of this H7N9 variant beyond China's borders possibly into Vietnam, North Korea, or a -stan
Click on graphs to enlarge.
Keep an eye out for H7N9 Outbreak #4 - coming to a colder China around November 2015. 

But for now, it might be time to hit the FluTrackers line lists (okay, I've had 4 tabs open for ages) and graph the course of another source of concern - H5N1 cases in humans.

Societal change and H7N9..

The importance of societal change for controlling infectious disease outbreaks really cannot be over-stated. 

For Ebola virus disease, it came down to stopping the tradition of direct contact with the body of those who have died and dircet contact in general. For MERS it
seems that occasional camel contact triggers insertion of the MERS-CoV virus into hospitals where lax infection prevention and control practices add to the case load. 

For influenza A(H7N9) virus cases, it is the habit of obtaining live poultry from retail markets where rare virus-laden chooks are culled and handed over because of a desire to see, choose and purchase the tastiest fresh chicken. 

There is a common thread among these stories about direct contact or inefficiently droplet-transmitting virus infections: we can stop their spread. 

But we also amplify and prolong their spread. 

However, when it comes to human-adapted, efficient droplet-spread or airborne-transmitted viruses - well, then we're in trouble. Of course we could all just lock ourselves in a room for a few weeks but that won't ever happen.

So its very important to head off these "emerging" viruses while we still have a modicum of control over them. Once they get away from that control, and theoretically that could happen in the blink of an eye-right now even-no amount of fancy infra red cameras, poorly donned surgical masks or fancy hospitals laden with machines that blink and go ping, will stop them from spreading globally.

Cheery.

In the meantime - here's hoping China speeds up the closure of those live poultry markets. Habits can be changed but death is forever.

Click on image to enlarge.

H7N9 outbreak #3 underway?

What better way to start 2015 than a snapdate!! For those who are new to them here on VDU, they were initiated here and defined here as snap updates - posts that don't have lots of detail and chat...although they almost always end up having lots of chat!

Figure 1. H7N9 cases by week of onset (or hospitalisation
or reporting dates of the preferred onset date was
not made public).
Click on image to enlarge.
This one is an update of the situation of one of the many avian influenza viruses ("bird flus" if you must) around again - avian influenza A(H7N9) virus, or just 'H7N9'.

In Figure 1, I've taken the huge liberty of adding in the start and end dates of the 3 outbreaks of H7N9 to date; and in doing so, I've said that China is in the early stages of one right now. I may well be wrong of course - this is a blog and these are my opinions - but it looks that way to me. 

Figure 2. China's northern laboratory network influenza
surveillance data up to Week 51 of 2014. [1].
Click on image to enlarge.
The case numbers for H7N9 in Figure 1 have been above zero for a little while and in particular November looked like a busy month (see weekly and monthly tallies here). Keep in mind that there is also a reporting lag - the time between date of onset (obtained from more detailed World Health Organization data) and the date the case was publicly reported (I rely on FluTrackers line list for these details). That delay can be a month or more on occasion; up to 38-days in late December. I suspect this is because China reports cases to the WHO in batches, something instigated toward the end of the 1st and 2nd outbreaks. So I suspect we will see more cases assigned to December, during reports that come out in January.

But it look like 'tis the season for influenza in humans in China (see figure 2 and the Chinese National Influenza Centre [2]) - and as some of us have discussed on Twitter, this is most probably due to the changes in weather (environmental conditions) which result in sustained viral survival on cough and sneeze-contaminated surfaces and in wet and dry propelled droplets and droplet nuclei; in both man and bird (see Hong Kong avian influenza detection report dates [3]). 

That sustained survival may well be all it takes for more of us to pick up an infectious viral dose.

Once the seasonal influenza viruses get a foothold in us, they spread well, causing disease in those who are susceptible and probably a bunch of unnoticed infections in those with previous exposure to that strain plus a healthy immune memory of that intrusion. By "seasonal influenza virus, I mean those that replicate in and circulate efficiently among humans, as opposed to the relatively inefficient avian subtypes.

So stay tuned to H7N9; it's not yet very good at spreading between humans but its established in birds and has been spilling over into humans since at least the beginning of 2013. We know how influenza can deal us a rough hand if the stars and its genetic segments align favourably (for it). Oh, and the continued reliance on fresh chicken obtained from and killed at live poultry markets. The majority of cases have very clearly had contact with poultry as defined by the WHO. 

References...

  1. http://www.cnic.org.cn/eng/show.php?contentid=738
  2. http://www.cnic.org.cn/eng/surveillance.php
  3. http://www.chp.gov.hk/files/pdf/global_statistics_avian_influenza_e.pdf

Influenza A (H5N6) virus in humans...

Provinces hosting human cases of H5N6
Adapted from [8]
Click on image to enlarge.
After late December's announcement of a human infection with another avian influenza subtype, H5N6. The tally of human infections by this subtype of FluA stands at 2 - that are reported anyway.

The ever vigilant @FluTrackers (and their line lists, news posts and commentary) and the always alert @Fla_Medic (and his Avian Flu Diary blog) have these cases well covered.

I just wanted to make a summary here for my own reference in making some slides for a talk next month.
  1. ~23-April-2014. [1,4,5] 49-year old male (49M) from Nanchong City, Sichuan Province.
    Acute severe pneumonia, died 5-May-2014
    Exposed to dead poultry
  2. 3-December 2014. [2] 58M from Guangzhou City in Guangdong province.
    Critical condition in hospital since 9-Dec-2014
    Exposed to live poultry but not ill contacts [3]
There have also been plenty of lethal animal infections by this and other highly pathogenic avian influenza (HPAI; referring specifically to the bird's outcome) subtypes and strains [7], including:
From an OIE Report 21-Oct-2014. [6]
  1. 12,000 quails in Quang Nai Province, Vietnam in 18-Dec-2014
    http://en.vietnamplus.vn/Home/Quang-Ngai-destroys-12000-AH5N6-infected-quails/201412/59394.vnplus
  2. 1,338 birds on a farm in Nanbu, Nanchoing City, Sichuan Province, China
    http://www.oie.int/wahis_2/public%5C..%5Ctemp%5Creports/en_fup_0000015698_20140731_162951.pdf
  3. 20,550 (17,790 fatal) birds on a farm in Shuangcheng District, Heilongjiang Province, China, 23-Aug-2014
    http://www.oie.int/wahis_2/public%5C..%5Ctemp%5Creports/en_fup_0000016060_20141024_193420.pdf
  4. Birds in Muang Nan and Muang Xayabouly Districts, Luang Prabang and Xayabouly Provinces, Laos in 12:14-Mar-2014
    http://wwwnc.cdc.gov/eid/article/21/3/14-1488_article#r4
No sign of anything like sustained human-to-human transmission of this viral subtype to date. But another for the influenza virus Rubik's cube.

References..
  1. https://flutrackers.com/forum/forum/china-h5n1-h5n8-h5n6-h5n3-h5n2-h10n8-outbreak-tracking/164419-china-man-49-with-acute-severe-pneumonia-died-from-h5n6-nanchong-city-nanbu-county-sichuan-province?t=222782
  2. http://www.who.int/csr/don/28-december-2014-avian-influenza/en/
  3. http://news.xinhuanet.com/english/china/2014-12/23/c_133874590.htm
  4. http://afludiary.blogspot.com.au/2014/05/sichuan-china-1st-known-human-infection.html
  5. http://www.promedmail.org/direct.php?id=2451125
  6. http://www.oie.int/wahis_2/public%5C..%5Ctemp%5Creports/en_fup_0000016060_20141024_193420.pdf
  7. UPDATE ON HIGHLY PATHOGENIC AVIAN INFLUENZA IN ANIMALS (TYPE H5 and H7) from the Office International des Epizooties (OIE), otherwise known as the World Organisation for Animal Health
    http://www.oie.int/animal-health-in-the-world/update-on-avian-influenza/2014/
  8. http://en.wikipedia.org/wiki/File:China_administrative_claimed_included.svg#filelinks

Influenza A(H7N9) virus: detection numbers and graphs...

This is a static page that will house my graphs of influenza A(H7N9) virus ("H7N9) numbers produced by the various Ministries of Health for the provinces and municipalities of China, the World Health Organization and FluTrackers.

They may take me a little while to get back up-to-date in this new format so stay with me. I will Tweet each update as I do for MERS-CoV and Ebola virus updates.

There is also an accompanying map page which for now is located here.


Reminders: 
  • The graphs above, as with all on VDU, are made for general interest only. They are also freely available for anyone's use, just cite the page and me please. The data can be downloaded by clicking on the "Download" link at the bottom-right of each dashboard. It may be that I have misinterpreted the language in the reports (sometimes a little tricky to wade through) or miscalculated some totals based on the way data have been presented.
  • In any outbreak, epidemic or pandemic caused by a know or emerging pathogen, the numbers presented publicly, and used in these graphs, are expected to represent only a fraction of all the cases that have and are occurring. This is just the nature of the imperfect biological'ness of these events.
  • I am only able to plot what is publicly available-you could do this too. No secret associations or back-room deals provide me with these data.

Now for something (not so) completely different: H7N9 maps...

Now it's time to mess around with influenza A(H7N9) virus mapping using Tableau.

I've (only just) realised the my esteemed peer, Shane Granger has been using Tableau to do this for ages (see here), and that this will be duplicating his excellent work. So I'll try my best to consciously differentiate my maps from his - but there's only so far you can go with that and there will be overlap. 

The page below is a very early first play with H7N9. It's just detections broken across 2013 and 2014, by province most likely to have been the source of the infections (as far as I can tell) in mainland China. 

If I can master this I'll try and add more details in the future. For now, these numbers a a little out of date but he trends are similar. This charts 449/452 detections.


Snapdate: Avian influenza A(H7N9) virus...

There seem to have been more announcements of late than previously so I thought I'd plot this and see. 

These are a little adrift as the last 7 or so have not been through the WHO scrubbing process (which adds extra bits of data) so we will see a little shifting the last 2 or so blue dots on the chart below.
Click on image to enlarge.

Guangdong and Anhui provinces have the most active case generators in May.

Anhui province has reported 3 cases in a week and there seem to have been a constant stream of cases in May, but they they don't, in reality, seem to be out of what's become the ordinary in 2014 for a virus that is happily ticking over in several provinces.


Avian influenza A(H7N9) virus found in more than half of wet markets in Guangdong...

It comes as no surprise to me, but is still a very welcome piece of data, that Guangzhou's ongoing live bird markets and concurrent continued cases of H7N9 in people, are also happening in a an environment of 60% of market stalls tested positive for the virus in April.

A report in the South China Morning Post noted 
"Upon conclusion of the trial on September 30, the city government proposes gradually extending the ban, covering chickens, ducks, geese and pigeons, to other parts of the metropolis. The ban is expected to be implemented citywide by 2024."

"Currently, it affects 298 live poultry stalls at 82 wet markets in Yuexiu district, and in parts of Tianhe, Liwan and Panyu districts, where vendors will sell centrally slaughtered chickens that will be provided by three designated suppliers."
This is welcome news and a positive step towards stopping not just H7N9, but a raft of other influenza viruses that jump to us from, and mix to create new virus within, birds.

Source...
  1. http://www.scmp.com/news/china/article/1505389/guangzhou-begins-trial-ban-live-poultry

H7N9 Snapdate: some quick charts...

Click on image to enlarge.
I don't have a lot of time tonight so this is just a quick post of some updated charts with a few summaries of some key features of the influenza A(H7N9) virus situation in south-eastern China. At writing it was at 432 detections with media reporting 128 deaths

Click on image to enlarge.
Guangdong is where H7N9 is still most active and it is this province that is the source of the continued cases trickling off Wave 2's peak.

Most H7N9 cases overall have been in Zhejiang and Guangdong provinces but lately, post-peak of Wave 2, there has been continued activity in Jiangsu province including a recent healthcare worker with no mention of "contact with poultry"; the absence of which stands out in World Health Organisation (WHO) reports because most cases are followed by affirmation of that phrase.

Click on image to enlarge.

In  the  survival chart above we see that most of the fatal cases, shown in red, are defined by an older age. Unfortunately, a lot more of the fatalities have been reported through the media without identifying details (48 of 128), than have come through official Chinese channels and out via the WHO. This lack of detail makes it impossible to clearly link a lot of the deaths to the case announcements. Only the custodians of these data know what this chart should really look like. NB: Since making the chart this morning I've found a handful more case details at FluTrackers, but public detail on fatal cases remains the weakest of any of the H7N9 data.

Click on image to enlarge.
We can see in the weekly chart on the right that the two H7N9 waves differed in timing, the width of their bases (more cases in Wave 2) as well as how "tight" their peaks were. Wave 2 has tailed off, but continues to spit out cases, while Wave 1 comprised both a steep climb and a steep decline in human cases.
Click on image to enlarge.

If we zoom in on Wave 2 we can see by looking at cases per day in the chart on the left, that between 0-4 illness onsets per day are being reported, as they have been since late Feb-2014. 

Is this the legacy of those regions whose live bird markets remained open or were only shut temporarily for disinfecting and restocking? Those regions with markets that were shut for much longer, or for good, do not seem to have contributed much to the continuing leak of H7N9 infections despite being key contributors during the peak periods before markets were closed.

Click on image to enlarge.
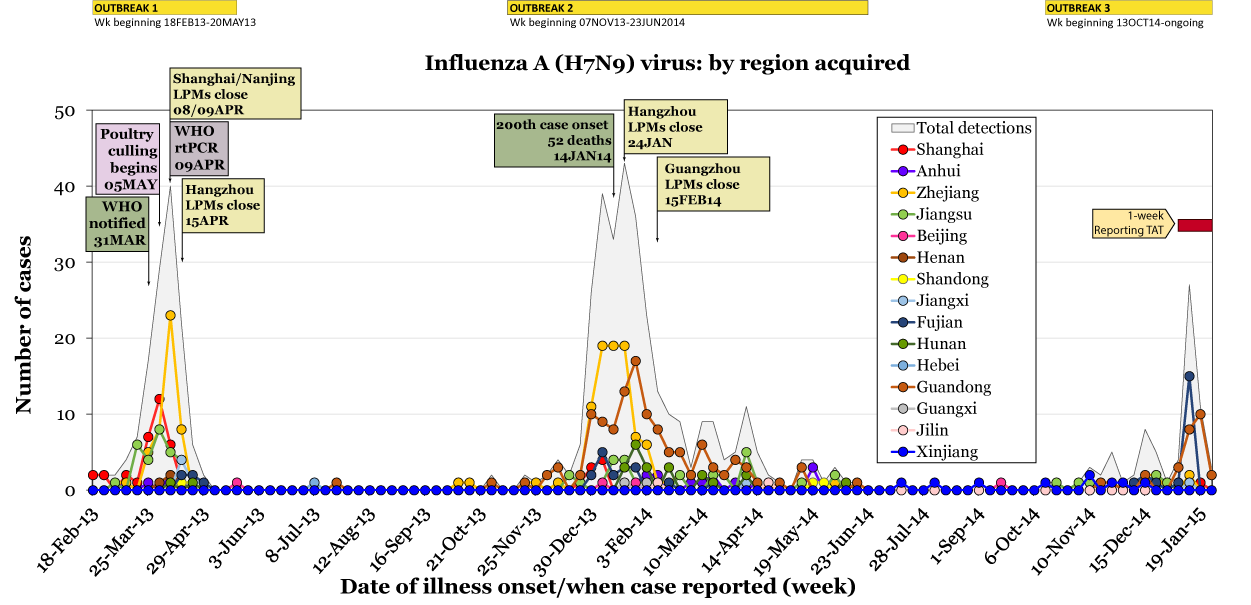
In zooming in on Wave 2's cases by week, but this time based on the region of likely acquisition of infection, we see that Guangdong province (brown line) has been the most consistent contributor of human H7N9 infections both late during the 2nd of the Wave 2 peaks, but also after the peak's decline almost everywhere else in south-east China. There was considerable publicised unwillingness from poultry producers to permanently close markets in this Province, a location with a major role in the nations poultry production. And so this little experiment incubates further and I have little doubt we will see the impact of that unwilingness late in 2014. 

Click on image to enlarge.
As noted above, public H7N9 death data do not allow good linkage with official case announcement data for about 48 fatalities, so my second-last chart tonight uses both public and media-release numbers to try and illustrate how the proportion of fatal cases (PFC) has changed across both Waves. The PFC seems to be holding fairly steady now between 17% and 30% (depending on source of numbers).


Click on image to enlarge.
And finally we see that the age and sex distribution across all cases (both Waves) is skewed to wards older males. Same as usual. If we look at this distribution (ran out of time to put in here) for the fatal cases, it is much more tightly grouped around the >60-year olds, but that females appear to dominate males in deaths during Wave 2, whereas it was the other way around for Wave 1.

Watching zoonoses evolve...

Special guest writer: @influenza_bio

For the first time in human history, we are watching diseases jump from animals to humans on a large scale. We've seen diseases appear for the first time in humans before; that's not new. We've seen HIV and several new strains of influenza emerge over the past century or so, for example. What is new is that we can now watch this process as it happens. We are able to watch animal diseases trickle case by case into humans, and we wonder whether any of these diseases might some day become human diseases. We wonder whether we might be watching pandemics develop in real time.

A disease that jumps from a non-human animal to a human (or the other way around) is called a "zoonotic" disease or a "zoonosis." Individual cases are called "zoonotic" cases. When a zoonotic disease is trying to make the jump to us permanent, we call this disease an "emerging infectious disease."

We have certainly been watching a lot of zoonotic MERS coronavirus and bird flu (e.g., H7N9 and H5N1) cases develop in people lately, along with Ebola virus cases. Zoonotic cases of other diseases, including infections with various strains of bird and swine flu, occasionally develop, as well, and are watched closely.

When the 2009 H1N1 flu pandemic started, we had no clue much beforehand that it was on its way.  We didn't even have surveillance data about swine flu strains that were even particularly close to the strain that emerged in us. A large animal flu surveillance gap blindsided us that year.

And we will undoubtedly be blindsided again by other emerging infectious diseases that we won't even see coming, although people are doing their best to see what's out there.

When an emerging infectious disease jumps to humans, it can cause either a relatively local outbreak or a worldwide outbreak, called a "pandemic." If a disease becomes a pandemic, that just means that it's spreading worldwide; the word "pandemic" doesn't imply anything about how bad the disease might or might not be. In some sense, the worst case can be when a disease jumps to humans and becomes "endemic" in humans, meaning that it gets established in people and regularly infects people, year after year. Endemic diseases can circulate worldwide (e.g., influenza) or in more restricted geographical regions (e.g., malaria).

Our knowledge and resources have grown to the extent that we are currently able to monitor some significant zoonotic outbreaks of disease. We are currently watching the MERS coronavirus and the influenza A(H7N9) virus both try to become human viruses.

Will either one succeed? We can't say. We've never watched this process happen before. We don't know how long such a process "usually" takes, or whether there even is a "usual" amount of time that it takes. We don't know how long it might take, or how quickly it has happened before. We doknow that the process is "stochastic," meaning that it involves a lot of chance. A pathogen that in one situation might cause a pandemic might just die out in another situation. Everything depends on the specific changes in a pathogen that get a chance to develop and on whether those changes end up getting passed on. We don't know how often pathogens "fail" when they "try" to make the jump to humans.

A lot of us have watched the recent surge in MERS coronavirus cases with some amount of concern. As of April 19, 2014, there are two large clusters of cases in the Middle East, and at least one of them is still growing. One cluster, in Jeddah, Saudi Arabia, now has 60 cases; 7 cases were added to this cluster today, and 6 were added yesterday. There are perhaps over a dozen cases in another cluster in the UAE. One patient who became ill with MERS in Jeddah at the end of March flew to his home country of Malaysia while ill and subsequently died in Malaysia; 79 of his contacts are now being watched closely in Malaysia. Test results are starting to come in for a number of these contacts, and thankfully all are negative for MERS so far. An asymptomatically infected Filipino health care worker traveled on an airplane back to the Philippines a few days ago. Yesterday, a MERS case was announced in Greece; a Greek man who had been living in Saudi Arabia was recently in Jeddah and presumably became infected there before flying back to Greece. He arrived in Greece with a fever; his contacts are now being monitored. In other words, MERS case numbers are growing quickly right now, at least in part through human-to-human transmission, and infected � and potentially infectious � patients are getting on airplanes to travel around the globe.

Does what we're seeing now represent changes in the virus that are making it more transmissible among humans? Or are we seeing a random fluctuation in the numbers of cases? Or, are we seeing more cases simply as a result of improved surveillance? I would argue that what we're seeing likely reflects one or more changes in the virus, simply because
  1. We've been seeing so many more symptomatic cases recently, 
  2. We've been seeing significantly larger clusters than we've ever observed before,
  3. A greater number of health care workers appear to be getting infected than ever before, and
  4. A greater proportion of cases are in health care workers than ever before. 
It's not that we've been seeing a rise only in the number of asymptomatic cases detected, which could suggest that we're only seeing the effects of improved surveillance. Moreover, while surveillance does seem to be picking up more mild and asymptomatic cases, it is difficult to know whether we are seeing more of these cases because of improved surveillance or because there simply are more such cases now. A lot of variables are being changed at the same time, and we don't have perfect information.

Nonetheless, the sheer numbers of recent cases suggest to me, at least, that the virus is changing and becoming more transmissible among humans. Until recently, we rarely saw evidence for human-to-human transmission of MERS; most cases may have been zoonotic. Now, however, large clusters involving roughly 1 to 4 dozen people are being seen, with single infected individuals infecting possibly up to a dozen or more other people. This is new. I don't think that we're seeing these clusters just as a result of improved surveillance, although I would be very happy to be wrong.

What does the future hold for MERS? We can't know. We might be watching MERS become a pandemic, and we might not. We might be watching the current relatively small MERS outbreak develop into a larger outbreak that eventually gets contained, as was seen with SARS. Or, the whole outbreak might all just simmer down or go away. Even if the virus were currently changing to become more transmissible, the current spate of cases could still simmer down or go away, just stochastically, just through sheer chance.

Prudence would dictate that we remain concerned and vigilant, however, especially as symptomatic MERS cases have had an approximately 40% case fatality rate (CFR). If MERS did cause one or more wider outbreaks in humans, that CFR might or might not change. Even if the CFR dropped to 10% of what it is now, it would still be on the same scale as the CFR for the 1918-19 influenza pandemic.

As a global society, we have an obligation to do everything in our power to prevent the MERS coronavirus from causing larger disease outbreaks in humans. We need more surveillance in affected countries, including much more genetic sequence data. And in countries of the Arabian Peninsula that are currently detecting MERS cases, infection control procedures need to be improved to the point where nosocomial cases in health care workers and patients are prevented. Health care workers in other countries should be educated about the possibility of MERS patients arriving from afar and about how to treat such patients safely. If this virus becomes more transmissible, we should not be caught unprepared. We can see this one coming.

Avian influenza A(H7N9) virus cases hit 400

While everyone was looking at Guinea and the Ebola Zaire outbreak, that stealthy H7N9 has gone and infected a total of 400 people that we know of. It is of course, just another milestone and not an indication of anything changed about the virus. In fact the trend for few cases per day is continuing. One constant in s sea of change and new things.

Another constant, the up-to-date nature of the FluTrackers case list - check it out here. 

I have to run - much to learn about Ebola!

References...

  1. FluTrackers H7N9 case list
    http://www.flutrackers.com/forum/showthread.php?t=202713


Any differences in the sex of avian influenza A(H7N9) virus cases in different areas of China?

a) Male (blue) and female (lavender) lab-confirmed H7N9 human cases broken into the Province or Municipality of likely acquisition. b) The proportion of total H7N9 positives at each site of acquisition that are female (lavender).  The proportion of females in Wave 1 (Range of weeks beginning 18-Feb-13 to 20-May-12) and Wave 2 (07-Oct-13:current) are also shown as a horizontal line for comparison.
Click on chart to enlarge.


This new chart idea was just a look-see at whether there is anything out of the ordinary about the sex distribution of H7N9 human cases in the different areas of China. These are total numbers from both Waves of H7N9 season.

I've included case numbers in Part a) as well as proportion of females in part b) to show that a value of 100% must be place in context of only 1 POS!

Nothing much to see here folks.


H7N9: the dotted lines that make sense of things...[CORRECTED]

Click on image to enlarge.
The latest H7N9 case-per-day chart shows that the trickle of human cases of confirmed avian influenza A(H7N9) virus infection is becoming a drip. The tap? My money is still mostly with the market closures. What precisely in the markets is the source of human H7N9 acquisition? Dunno, but the consensus seems to be poultry; songbirds also look pretty good though. It doesn't have to be, and is unlikely to be, just 1 thing of course. We know that this virus, as with other avian influenza viruses, can be shared around among bird species. It can even go into a human and that isolate be used to infect a bird again. See my recent post on some of this.


Click on image to enlarge.
What's also particularly intriguing, among the many interesting aspects of H7N9's acquisition and spread among humans, is that we're seeing much more "shouldering" in the Wave 2 epidemic curve than we did in Wave 1's.

Instead of the precipitous decline we saw back in 2013, we're seeing a drop down to ~10 cases per day, but then a slower decline the rest of the way. Is this because we started human cases from more sites this time around?; because markets took longer to close after the cases numbers began to climb?; is it related to markets being closed at different times, in different ways, in different locales? Who knows?
Cases by region acquired, per week, with different
 regions highlighted by coloured lines and the 
total case number in the background (grey).
Wave 1 and Wave 2.
Click on image to enlarge.

Dr Katherine Arden suggested I have a look at what's happening in each Province or Municipality and see whether any particular place can shoulder the blame for the shouldering. And that does seem to be the case if you look at the adjacent chart. Guangdong province seems to be the major culprit contributing to the shoulder effect. 


Cases by region acquired, per week, with different
 regions highlighted by coloured lines and the
total case number in the background (grey).
Wave 2 only.
Click on image to enlarge.
In the zoomed-in version that focusses on Wave 2 alone, we can see that the Wave 2 "peak" has in fact 2 peaks; the 1st peak dominated by Zhejiang province cases and the 2nd driven by a surge in Guangdong provincial cases. Guangdong cases took longer to drop away, and are in fact still being reported, possibly because the major poultry markets there were closed later than in Shanghai and Zhejiang province and only temporarily for a clean. Or perhaps the bird outbreak @influenza_bio and I discussed has a source in Guangdong province?

It's all speculation beyond the data we can actually plot.

The decline of H7N9 Wave 2: some thoughts on why it may be different from Wave 1...

Influenza virus and influenza the disease certainly give scientists a run for their limited money when it comes to predicting what either will do from year-to-year, country-to-country or outbreak-to-outbreak. 

And just when you think you know enough, things change. 

This morning my Twitter stream was fed by a sparkling rivulet of informed comment by @influenza_bio ("A biologist"; follow him if you don't already) on the subject of why H7N9 cases are falling. @influenza_bio groups together a few great points:
  1. H7N9 cases are declining.
    Agreed, I think Wave 2 ended almost a month ago.
  2. Overall, influenza-like illness (ILI) visits in China have declined.
    A clear parallel, but is it causal? ILIs provide a general guide to influenza circulation (general, because other viruses cause ILI which is basically fever + upper and or lower respiratory signs and symptoms - so a very broad but useful good guide
  3. Is the drop in human H7N9 cases linked to the end of a (silent) outbreak in birds (poultry, waterbirds, songbirds, both...)?
    Finding data on specific bird migration dates in the region is difficult. See here and here for some generalizations. Seems very reasonable.
  4. Live bird market closures cannot be the only cause of a drop in H7N9 cases otherwise we'd expect to see cases in other areas continue to rise (presumably areas where markets are not closed).
    If we compare Zhejiang to Guangdong, then we can see that the delay in closing Guangdong's bird markets seems to have manifested as a delay in slowing of human cases; most recent H7N9 case acquisitions have indeed been in Guangdong (a major poultry producing area in southern China) whereas cases in Zhejiang which, like other eastern coastal regions shut their markets earlier and "permanently", generally speaking, have dried up.
  5. If H7N9 human case decreases were linked solely to weather, then how could we explain the peak in 2013 which extended into late April whereas it looks to have peaked well before that, in early Feb, in 2014?
    Given that the seasons have not differed between the years (or have they?), I'd suggest we look more at the start of the 2 Waves; Wave 2 commenced earlier in 2014 than did Wave 1 in 2013, but the precipitous decline of both outbreaks of human notifications seemed to have been more closely tied to market closures than dates on a calendar. Of course markets are stocked with H7N9 infected birds and that which links to outbreaks at the supply end unless poultry acquired their infections at markets and then spread that between markets by bird movements which can extend right across southeast China. Why did it start earlier is a key question for me.
@influenza_bio finishes with the comment that...

As I've learned from @influenza_bio, many factors go into humans acquiring a particular influenza virus at a particular time/season, and probably no single thing is responsible for all events for any given outbreak. Phew. But that's why we don't have influenza infections all the time and it underpins why they peak at a certain time.

Human acquisition of influenza virus is related to:

  • How a person is exposed to the virus (aerosol from upper respiratory tract coughs and sneezes or self-inoculation from contact with contaminated surfaces)
  • Whether the virus survives long enough to be inhaled/self inoculated which is in turn linked to virus subtype and strain and environmental temperature and humidity (see some more on that in a guinea pig model here)
  • The host and their immune state and general health, smoking, underlying diseases etc
  • How much virus enters the host and where it "lands" and makes a footing in the host's respiratory tract
  • The spaces we share with infected people and how fast and well the air is filtered/exchanged in those spaces
  • The virus subtype in terms of what receptor it prefers and where those might be located throughout the respiratory tract.
  • For avian influenza in humans there is also the type and length of exposure to the animal hosts and their environment

Not an all inclusive list I'm sure, but you get the point. Influenza viruses are a complex beast, made more so by the fact that any given subtype could be represented by a range of strains indicating a variety of stabilities, preferences for receptors, antiviral susceptibilities etc. 

So I complete agree with @influenza_bio, more bird surveillance would indeed be a very important step in understanding what is happening in and perhaps predicting the risk of, human outbreaks of this and other avian influenza viruses.

An update on avian influenza A(H7N9) virus cases in humans: Week 56

As we currently stand (this minute), there are 389 laboratory confirmed human cases of infection including perhaps 122 deaths (31% PFC). 

H7N9 cases are mostly noted in older males (Average age 54-years; Wave 1 57-years; Wave 2 53-years) with the major risk being exposure to birds and "poultry markets" (commas because it is not just poultry being sold at these markets). No sustained human-to-human transmission has been noted and no specific vaccine exists although one is coming soon apparently. Oseltamivir or zanamivir are useful antivirals while adamantanes are of no use because H7N9 is resistant. to them. The second wave has peaked but we are still seeing a shoulder off the main peak from Wave 2; smaller numbers of cases each week (no longer occurring every day), often from regions other than those with closed poultry markets or with only recently closed or temporarily closed markets.


First chart.
Click on chart to enlarge.
First chart: where is H7N9? It's in Southeast China, most cases having been acquired in Zhejiang province (139/389 cases; 36%) during both Waves of human infection and Guangdong province is currently a very close second place (95/389 cases; 24%).


Second chart.
Click on chart to enlarge.
Second chart: where has H7N9 been focused over time? We can see from this chart that Zhejiang and Guangdong provinces have accrued H7N9 cases most rapidly. While Zhejiang featured in both waves, Guangdong is of Wave 2. It will be interesting to see what happens if there is a Wave 3; without finding and controlling the source of human acquisitions and if the birds with the virus continue to have the virus, I expect we will see future waves.


Third chart.
Click on chart to enlarge.
Third chart: the waves of an outbreak. Wave 1 was 2013 while Wave 2 started in Oct-2013 but really kicked off in Jan-2014. Cases dived in Feb-2014 but there are still sporadic cases being reported each week. The Week (#53) beginning 17-Feb-2014 saw 8 cases followed by 7, 4 and 0 for subsequent weeks. Keeping in mind that there are around 4-12-days (currently averaging 8-days overall) between onset of illness and when a case get confirmed by a laboratory (or reported publicly if no specific lab date is available), we may see a few more cases assigned to the last week of February yet.


Fourth chart.
Click on chart to enlarge.
Fourth chart: Age and sex of H7N9 cases. The age pyramid shows a decidedly upside down pyramid indicating that H7N9 disease is one of the older age bands. It also shows that it is a disease of men morseo than women.


Fifth chart.
Click on chart to enlarge.
Fifth chart: age by week and proportion female. This is an interesting one. There was a dip in the proportion of female cases for the week the week beginning in 3-Feb (right hand y-axis) which bounced back up a week or two later. 

Sixth chart.
Click on chart to enlarge.
Sixth chart: H7N9 cases per day and the rolling average. The decline in Wave 2 cases continues with multiple recent days recently in which no new cases occurred.

Like Us

Blog Archive