Medical News Blog Information

Advancing Emergency Care partnership in Ethiopia

Nov 14, 2014 � Three weeks and dozens of meetings later, still much remains to be done. For those who missed my earlier post, I have been in Addis Ababa, Ethiopia, working during my combination vacation-elective to help forge a network of Ethiopian Emergency Departments (EDs) in order to aid in multicenter data collection and analysis, and national and regional policy reform.

Right off the airport tarmac, it seemed, my early meetings proved even more successful than I had hoped. My desire to fashion a collaborative multicenter ED research network in this rapidly developing nation found strong buy-in from local leaders both in the Department of Emergency Medicine at the country�s flagship government hospital as well in as the Ministry of Health. By the close of week 1, we had assembled not only a team, but a detailed plan for how to collect existing standardized ED and hospital data at all government hospitals in Addis Ababa, as well as how to enhance ongoing data capture and analysis.

United Nations Conference Center, amidst
ubiquitous construction in Addis.
 It was fitting, then, that these early successes forging relationships across a capital city would be followed at the heels closely by the chance to observe how partnership is taking place across Africa�s Emergency Medicine community�at the Africa Conference on Emergency Medicine�s (AfCEM), a biannual event hosted this year at Addis Ababa�s United Nations Conference Hall. I had conveniently planned my trip to Addis to overlap with this four-day event. With great excitement, some 600 individuals from across the world crowded into the hall: researchers and clinicians, faculty and some of Africa�s earliest Emergency Medicine residents. All corners of the continent were represented. Old friends reunited, but just as many new hands were being shaken as well.

Plenaries and poster sessions provided much food for thought, and bold Ethiopian coffee additional mid-morning stimulation. Research samplings ranged from pre-hospital care and emergency medical dispatch, to components of emergency medicine residency education development in Africa, to assorted estimates on the burden of emergency disease in the region and world. Interesting as they all were, it struck me�as I volleyed from room to room as between buffet tables�that much of the research presented was the fruit of bilateral institutional partnerships, planted years ago through ad hoc personal connections and nourished over time into formal agreements between two institutions (one African, the other often US or Canada). Not discounting the importance these collaborations have had on advancing our specialty across this continent, I wondered whether the bilateral model is most indeed the most effective one for building cohesive systems of emergency care going forward. Indeed, while these partnerships have yielded tremendous gains for the hospitals involved�particularly in the formalizing of Emergency Department infrastructure and training of specialized practitioners�those majority of government hospitals outside the contracted bounds of bilateralism have been left to evolve asynchronously and independently. I had observed this in Addis Ababa the prior week, in my tours of ten government EDs, and I saw it at AfCEM in the subtle dis-ease expressed by current and recent highly-skilled emergency medicine residency graduates from across Africa as they anticipated careers in facilities without the financial, technical, or research support of their training institution. It is no wonder all of them want to stay at their hospital of training!


AfCEM coincided with the graduation of several
of Addis Ababa University's second batch of
Emergency Medicine residents, many of whom I
first met two years ago. The future leaders of EM
in Africa, whom I am privileged to call friends.
It is my hope that our work in Ethiopia may yield not only data useful to the profession of Emergency Medicine in this oldest African nation and across the continent, but may also serve as a model for how collaborative research networks can be built and managed by the African public sector, to the benefit of the entire system of facilities. Moreover, I hope that as this network grows in both the number of facilities and volume of patient data gathered, we might be able to open it for use by local residents and faculty�the future of African Emergency Medicine leadership�so that even as they spread to disparate facilities they might continue to work together as a team to advance the specialty through collaborative inquiry.

Conference drew to a close, and amidst all the hand-shaking and finger-foods I picked up a nasty upper respiratory virus that left me febrile and bedridden for two days, and submersed in my sinuses for the rest of that week. Week 3, therefore, started far slower than I had hoped, and government speed bumps cast further delays. And yet, even if slowly, progress continued to move forward. Much of what we had hoped to accomplish would need to be postponed until after my departure, but perhaps that was not a bad thing. After all, if this is to be a truly effective partnership�indeed, if it is to be an ultimately locally-run venture�most progress will need to continue even when I am gone. I can think of no more competent a team than my local collaborators (now quite close friends!) whom I have left behind. Their enthusiasm, their curiosity, their ambition for this project has fueled my excitement.

One of the ten hospitals visited in Addis
 Now back to good health, these final days have seen the development of several updated data collection templates that will now need to be mass-printed and distributed to all government hospital sites. Together, we have analyzed existing holes and quality gaps in current data collection and designed improved systems to fill them. We have talked with some hospital leaders, and will extend the invitation to others. We have pored through variables, designed research questions, and drafted study protocol. We have laid the groundwork so that this network can be disseminated even outside Addis.

As I sit in the airport now, reflecting as I make my way back to Boston, I must reiterate my immense gratitude to the Partners Centers of Expertise for their largesse in funding my travel on this exploratory venture. Although I came to this nation with merely a vision, a dozen and half contacts, and some scattered words of Amharic, three exhilarating (and exhausting) weeks later I feel I am leaving with much more. It is my hope and that of my collaborators that this trip is merely a prologue to a much longer story. Thanks for reading!

Dave Silvestri,
Department of Emergency Medicine
Massachusetts General Hospital

Brigham and Women�s Hospital

Point of Care Ultrasound in Rwanda : A few interesting cases.


Case 1:  Last week, we had a patient who presented to the emergency room booked as heart failure.  He was transferred from a district hospital with hypoxia.  The team there had started treating him with a beta blocker and Lasix but he was not improving.  His oxygen saturation was 76% on RA and 90 on a NRB.  His HR was in the 60's ( B-blocked), and he was midly hypotensive with SBP in the 90's.  His chest xray was clear without pneumonia or pulmonary edema.  Given his Hypoxia, the resident suggested we perform a point of care Ultrasound ( I was so happy he initiated this Ultrasound ).  A formal ultrasound could take up to 2 days to obtain, and with the rate of patient turn over at this hospital, who knows if patient would last that long.  His Bedside Cardiac Ultrasound showed  a severely dilated RV and a large dilated non-collapsing IVC ( sorry the other videos won't download, so only one cardiac view).  We of course suspected a pulmonary embolism in this patient.  We performed bilateral point of care 2 zone DVT studies which were negative.  Emergency team decided to heparinize this pt given these findings.  This week I checked on him and he was off oxygen and sitting up breathing comfortably waiting for a bed on the medical service.  Never got CT PE...family could not afford to pay ( you pay for everything at this hospital...including the gloves that clinicians use to care for the pt).  No money, insurance = limited care. 

Case 2:  Young male in his 20s who had a motorcycle accident presented from District hospital with minor pelvic fracture.  It took him about 2 days from his trauma before he presented to our referral hospital.  He complained of severe abdominal pain with us.  He was scheduled for a CT scan of his abdomen but it was taking a while.  We performed  FAST ( Focused Assessment with Sonography for Trauma) on him and saw this.  Yeah....That's a ruptured bladder.  He got antibiotics and a Urology consult. They requested a CT scan which happened 2 days later and confirmed a bladder rupture.  He was then discharged with antibiotics, a foley and was scheduled for outpatient cystogram...This basically motivated the residents to do FAST's on all traumas even if transferred 3 days after injury!!!!!  This helps form habit....and the residents get to perfect their Ultrasound skills.  


Case 3

This is a necrotic leg...This woman's leg has been like this for a few months...why did she not appear that ill???...Well Doppler U/s of the vessels of her legs showed a femoral arterial clot but also incidentally bilateral DVT's which probably prevented severe systemic illness.  She had bilateral DVT's due to large pelvic mass. She ended up having her leg amputated and last time I checked she was doing well on the surgical service.  Unclear what work up she would have for her pelvic mass.    


Soooo Much Pathology here...Because CHUK is the referral center in Rwanda and has the only public CT scanner ( other one is at a private hospital and you need lots of dinero), we get everything at this hospital.  On any given day we have many positive FAST's, large pericardial effusions, and cardiomyopathies.  Great learning cases!!  These were just a few. Thanks for Reading

~Phindile Erika Chowa MD
Emergency Medicine Residency, MGH/BWH, PGY3 ?

Toward Emergency Department Integration in Ethiopia


In the dark of the night, our plane descended. A galaxy of yellow and orange house lights swarmed below, drifting closer to my pocket of airplane window. Twenty hours of travel (including two brief layovers) was nearly over. Complimentary glasses of red wine (for the circadian adjustment) had done their trick, and our wheels skidded down on cool Addis Ababa tarmac like a reunion of old friends.

Just three years previously (in November of 2011) I made my first trip to Ethiopia, as part of a multinational study assessing medical and nursing students� migration intentions. At that time I partnered with senior educators in Addis Ababa University�s School of Medicine and worked closely with senior and junior students alike, making quick and close friends at all levels. Ethiopia had felt a strange and unfamiliar place to me then�far different in culture, climate, history and language than any sub-Saharan African place I had ever visited. Now three trips later, however, it was almost a second home, my friends here some of my dearest, and the culture and customs no longer new.

As I waited in line for a renewed visa, watching disembarking passengers bolus past outnumbered Ebola screeners, excitement and impatient apprehension both swelled as I began to unlock the mental list of immediate �to-do�s� needed to jumpstart the upcoming three weeks of work. No longer studying health professional student migration (as I had my first two trips) or working clinically in the Emergency Department (as I had my third trip), my goal this trip was to forge a network of Ethiopian Emergency Departments in order to aid in multicenter data collection and analysis, and national and regional policy reform.

As elsewhere across sub-Saharan Africa (and, in fact, throughout low- and middle-income countries), the importance of emergency care is growing. And while most Disability-Adjusted Life Years (DALYs) in sub-Saharan Africa are still lost to lower respiratory tract infections, diarrheal disease, HIV/AIDS, and malaria (by Global Burden of Disease data), the burden of traumatic injury and acute presentations of non-communicable ailments is rising.

Ethiopia, in particular, finds itself in a unique situation. With the 13th highest population in the world (second in Africa only to Nigeria), it also has both the largest proportion of rural inhabitants (80%) and the highest rate of urbanization (5%) of any of these most populous countries. But that�s not all. Among these most crowded nations, Ethiopia continues to boast one of the highest per capita GDP growth rates. In other words, Ethiopian cities are growing faster than in any other most populous nations (urbanization rate). Additionally, they will likely continue growing for longer than anywhere else, given the proportional and absolute size of the rural population, and they are filling with people who now have somewhat more money than they did, say, a decade ago. This money is often sufficient to afford slightly less healthy lifestyles (diet, cigarettes, etc.)�but not ample enough for medications to control the corresponding resulting chronic diseases. While these trends are familiar across Africa, it is in Ethiopia where a �perfect storm� of demographic and economic realities have rendered them most pronounced in both absolute and relative terms.

 For Ethiopia, the encroaching high tide of emergency care need represents both an immense crisis and an unprecedented opportunity. For a nation so historically rural, the urban health system capacity�including its emergency care capacity�must be rapidly expanded if it is to have any hope at absorbing the influx of demand. But precisely because so much growth is needed all at once, there is great advantage to undertaking it in a coordinated fashion. Indeed, it is in hopes of helping coordinate the emergency care data collection systems that I return to Ethiopia.

My first few days consisted of logistical essentials: buying a phone, buying a SIM card, buying a second SIM card when the first SIM card didn�t work; checking into a cheap hotel, moving to a second hotel with more reliable internet and closer proximity to the hospital; scheduling meetings, preparing documents for said meetings, rescheduling meetings, defaulting to back-up plans when rescheduled meetings fell through�. And finally came the opportunity to sit down with the Head of the Emergency Department (one of the hospital�s busiest men)�in a small hidden conference room tucked behind three bustling ED rooms. I handed him my proposal. We talked. Our meeting was brief; it didn�t need to be longer. We saw eye-to-eye�our mutual appreciation for the importance of this task fueling each other�s excitement. Without delay, he introduced me to an individual who would become over the next several days one of my closest collaborators�a young nurse
manager (A.Y.), recently trained in emergency care and critical care nursing and now working to coordinate referrals between Addis Ababa�s government hospitals.


As week 1 came to a close, I had spent many long days venturing with A.Y. and his team to all of the city�s government hospitals (as they coordinated referrals between them), confirmed data recording systems at each one, and developed a plan with A.Y. to standardize inconsistencies going forward. It was time for the next important meeting�with the Ministry of Health.

Over aromatic black Ethiopian coffee, we sat and pored through an intricate spreadsheet I had assembled on my computer late the previous night, summarizing the full week�s findings. The cool morning air bowed to midday sun, and we switched tables to keep talking. The lunch crowd came, then left. And still we talked through further details. Reviewing variables, considering how to improve collection of still others, discussing which additional ones might even be added going forward�and how, logistically, in a network of government hospitals with universal paper charts, to accomplish these tasks. Our work, at last, was finished. A team was formed. And week 1 in Ethiopia was complete, far more successfully than I could have imagined, thanks in large part to the Partners Centers of Expertise Global Health Grant.

Dave Silvestri, PGY-2
Department of Emergency Medicine
Massachusetts General Hospital
Brigham and Women�s Hospital


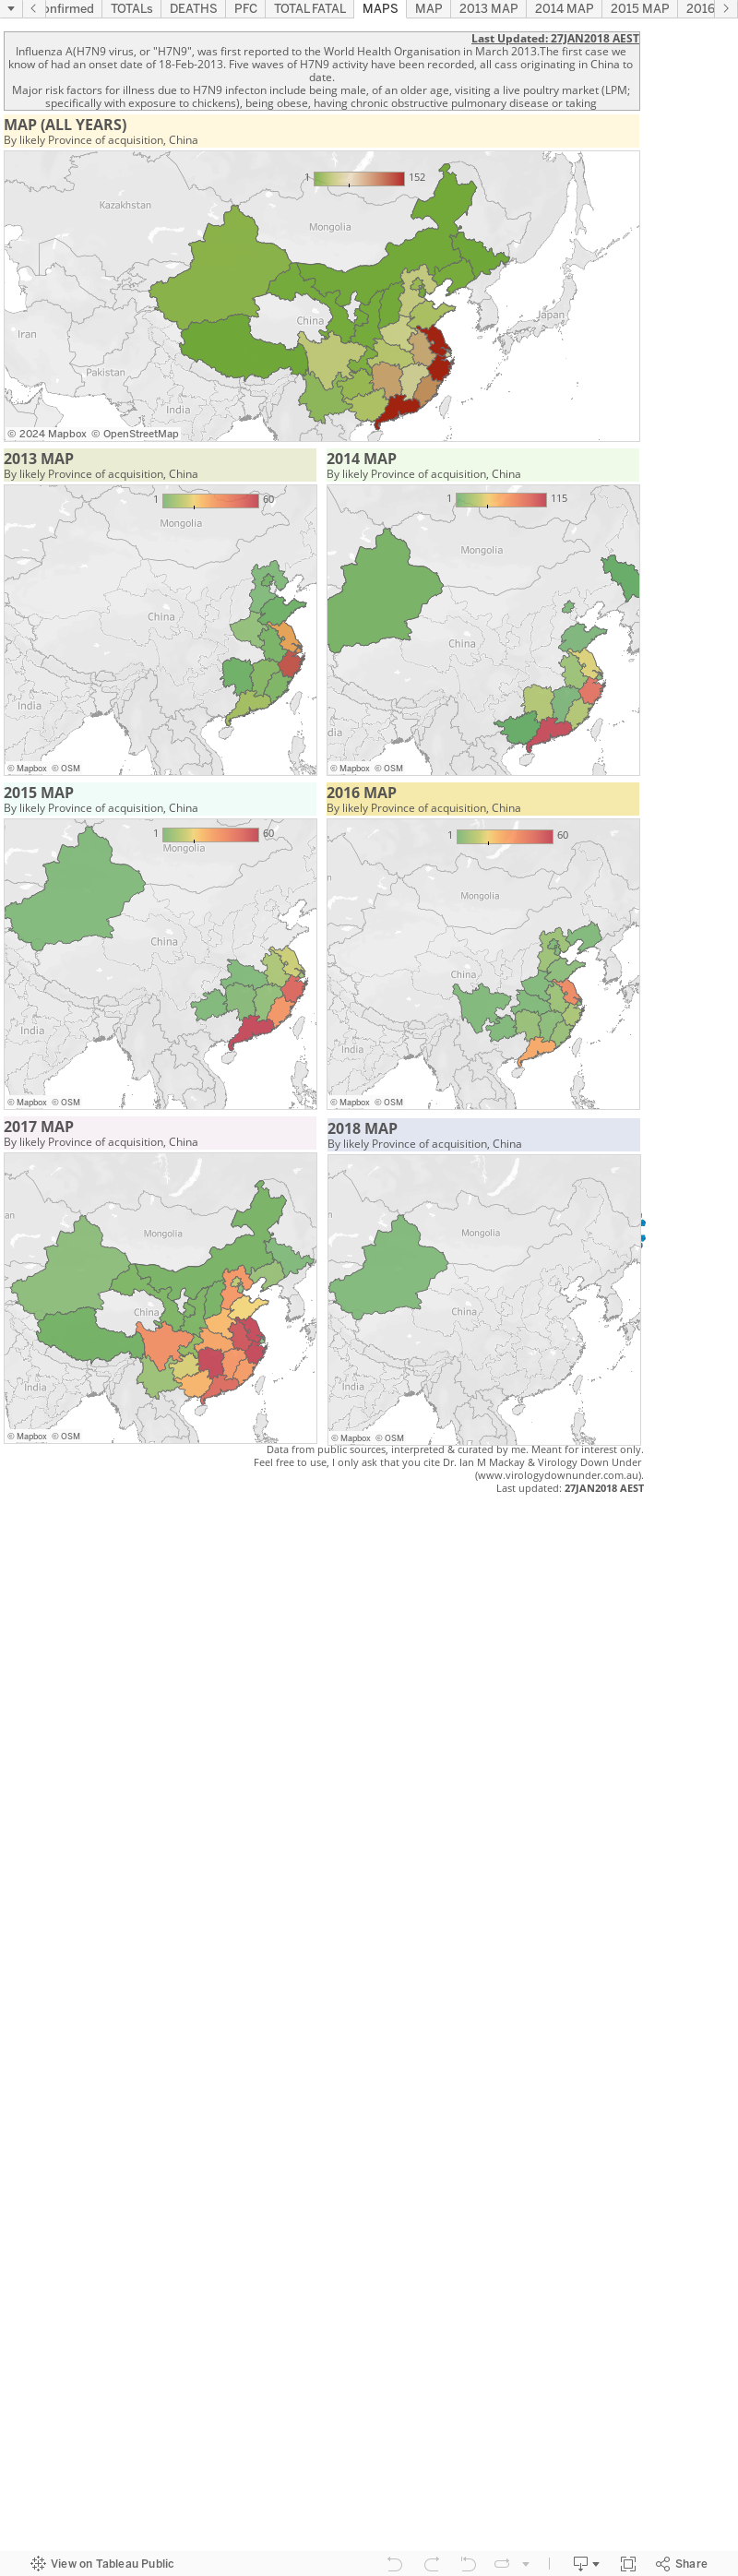
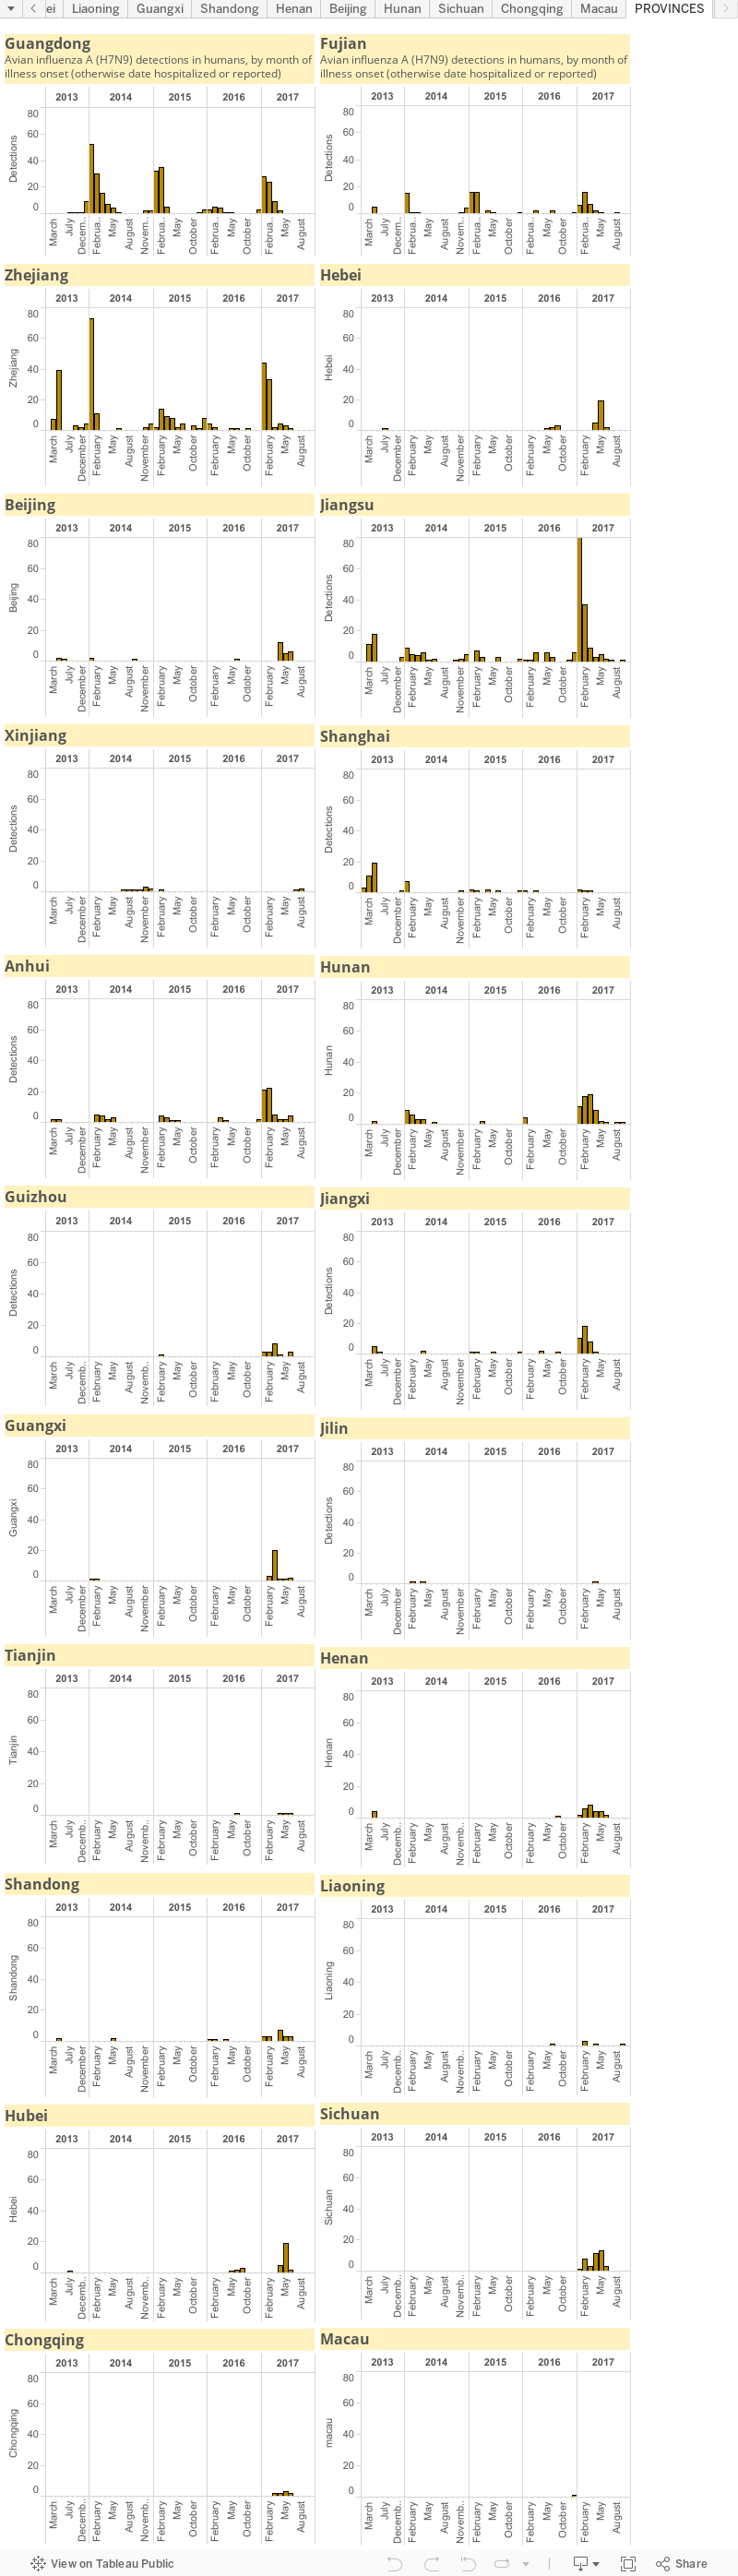
Influenza A(H7N9) virus: detection numbers and graphs...

This is a static page that will house my graphs of influenza A(H7N9) virus ("H7N9) numbers produced by the various Ministries of Health for the provinces and municipalities of China, the World Health Organization and FluTrackers.

They may take me a little while to get back up-to-date in this new format so stay with me. I will Tweet each update as I do for MERS-CoV and Ebola virus updates.

There is also an accompanying map page which for now is located here.


Reminders: 
  • The graphs above, as with all on VDU, are made for general interest only. They are also freely available for anyone's use, just cite the page and me please. The data can be downloaded by clicking on the "Download" link at the bottom-right of each dashboard. It may be that I have misinterpreted the language in the reports (sometimes a little tricky to wade through) or miscalculated some totals based on the way data have been presented.
  • In any outbreak, epidemic or pandemic caused by a know or emerging pathogen, the numbers presented publicly, and used in these graphs, are expected to represent only a fraction of all the cases that have and are occurring. This is just the nature of the imperfect biological'ness of these events.
  • I am only able to plot what is publicly available-you could do this too. No secret associations or back-room deals provide me with these data.

The bad the worse and the over-interpreted...

EVD case numbers between WHO reports. 
The World Health Organization (WHO) Ebola virus disease (EVD)case numbers that came out on 29-Oct were pretty big (see graph on the left). As if there weren't already enough new cases and deaths every 2-5 days, now there is this bolus of 3,562 cases added to the total. And a net change in deaths of -2? What the heck?  

Let's see if we can add some context.

According to a number of past WHO reports, a lot of effort has been going in to trying to collect data more effectively including improving the linkage of lab results to cases, cases to deaths, lab data to deaths and probably a million other things. 

Dr Bruce Aylward
http://www.who.int/dg/adg/aylward/en/
In the previous Roadmap SitRep and Roadmap update, the Liberian numbers did not move - they even had the same date. That was new and it was concerning because it suggested that reporting had been stopped or collapsed entirely. However this new large download of cases is in some way good news because it suggests reporting is working and the systems and processes are coping - although undoubtedly still stressed - again. 

The thing to be aware of is that these are not cases that have all been detected or all occurred since the last report 5 days previously. According to Dr Bruce Aylward, WHO Assistant Director-General, Polio and Emergencies, during a preceding media conference (and my thanks Martin Enserink for asking the important question; underlining is mine)..

In terms of the jump in the number of cases, one of things that we've talked about in the past on this is that with the huge surge in cases in certain countries, particularly in September and October, people got behind on their data.
They ended up with huge piles of paper in terms of cases, etc, and we knew and I actually said to you the last time, we are going to see jumps in cases at certain times that are going to be associated more with new data coming in but it's actually on old cases.
And a couple of days there were about 2,000 additional cases in, if I remember correctly, it was actually the Liberia case report but most of these were old cases because remember they got swamped a couple of months ago with a lot of new cases and just got behind on their data, so a lot of that is about reconciling new data.
If we look at sort of a seven day rolling average number of cases which have been around 1,000, just under that, about 900, there hasn't been a big change in that in the recent weeks.
So the 3,562 cases come largely from the past as well as the present. It's not that the sky has fallen in the past 5 days. Which is good news. But of course, that puts us back to "just" 1,000 or so Ebola virus disease cases a week. In other words, in just 1 week there are more cases than in any individual outbreak since 1976. 


The cumulative EVD case curve at 29-Oct
However, this week has seen a few articles and comments noting that the number of new cases in parts of Liberia seem to have fallen slightly. 

This seems to be a real trend in that there are fewer burials and more empty treatment beds and fewer cases found when sought in the community. Why there are fewer is not precisely known and it is far to early to rely on this yet. But we do know that there are better numbers of safe burials, better education, more experience with the disease, more help and facilities and more PPE comapred to when this started. 

The three countries with intense transmission still require a lot of help from us though - that urgency must not let up. Remember that cases had dropped a lot back in May - and now look where we are.  

If you can't get there in person to offer specialist help, and most of us cannot, keep bringing the issue to the attention of your country's leaders, learn about the virus and the disease from trusted sources and help teach others and head off ignorant comments, and donate some (some more) money to those groups who can make a real difference on your behalf (I've listed some great options here). 

Fighting the fire at its source is still the best way to help save lives in Guinea, Sierra Leone and Liberia and to stop new outbreaks from occurring in other countries.

References..

  1. WHO Ebola Roadmap SitRep#10
    http://apps.who.int/iris/bitstream/10665/137376/1/roadmapsitrep_29Oct2014_eng.pdf?ua=1
  2. Virtual Press Conference transcript
    http://www.who.int/mediacentre/multimedia/vpc-29-october-2014.pdf?ua=1

Point-of-Care Ultrasound Training for Emergency Medicine Residents in Kigali Rwanda

October 30, 2014

I am so grateful to have had the opportunity to join the PURE Team here in Rwanda and thank the Center of Expertise in Global and Humanitarian Health for making it happen.  PURE stands for Point-of -Care Ultrasound in Resource limited Environments and was created by a rock star former Harvard Emergency Medicine resident Dr. Henwood.  When Dr. Henwood gave a presentation on the impact of Ultrasound in resource limited settings her senior year, I knew that I wanted to not only perfect my ultrasound skills, but to also provide a useful skill to the practitioner abroad who sometimes may feel helpless when CT or Xray is not readily available.

Day 1
I survived a long trip to Kigali, Rwanda.  The view from the plane was amazing.  The landscape reminded me of my days as a child living in Swaziland.  I was picked up from the airport by one of the team members and given a short tour of the city before going home and crashing.  The people were wonderful and I even learnt a few greetings in the local language.

Day 2  We packed up the rental car to go to a district hospital about 2.5 hours away to give a training on Cardiac ultrasounds, FAST, and DVT ultrasound.  We drove up a windy road on a mountain ( mountains are very common here) where my heart literally wanted to jump out of my chest.  The view was amazing.

Unfortunately, the car broke down some where near the top of the mountain.  Within 30 minutes we had the local people call for the local mechanic.  The mechanic came on bike from Lord knows where and he diagnosed our car with an "engine problem" and called for the local tow truck to tow the car back to Kigali.


We paid about 300 US dollars to be taken back to Kigali Rwanda and to have the car towed-my pockets hurt still. It ended up being quite the experience, but somehow we had a wonderful day.  We met new people, saw a new place and broke bread together in the car.
After working in a few places in Sub-Saharan Africa one must be super flexible and adaptable, things happen and you must make the most of it.  I honestly had no complaints about this day.

Day 3
Okay finally work!!  We arrived at the University teaching hospital of Kigali at 8 am.  Our work is performed in the emergency and accident ward mostly, but other internal medicine, surgical and pediatric wards have requested to have scanning sessions for their residents.
 This ward serves a slightly different purpose than the emergency room in the US.  Most patients present from referring district hospitals and this can even be a matter of several days before arriving here.  I was told the role of the ED, is changing though with new emergency residents training in the hospital.  Our job is to teach and help facilitate scans with them and internal medicine, and surgical residents.  We in no way are here to take any role in patient care.

This day was busy, but apparently it gets more busy than this.  We had a number of scans in the morning. For example, we performed an ultrasound on pt who had known cardiomyopathy who presented to the hospital with shortness of breath.

The staff only had an xray from 1 month ago that they continued to refer to the size of the pt's heart.  For whatever reason, xray could not be performed that day.  We had the residents grab the US machine and look at the pt's lungs and heart.  He had bilateral pleural effusions, and diffuse B-lines likely representing interstitial edema.  His heart was globally dilated and had extremely reduced function.  The residents performed the scans and proceeded to treat the pt for a CHF exacerbation.

 We also had a trauma come in from the scene with GCS of 3.  One of the stellar training Emergency residents, ran the trauma.  A-B-C's initiated.  Pt airway was secured with ETT, He had a flail chest and decreased Breath sounds on the right and had a chest tube placed, and he was hypotensive and bradycardic.  His Pelvis was unstable.  The Emergency resident immediately called out for the US.  This was not typical in the past as part of the initial trauma evaluation, but the residents who are so excited about ultrasound have been incorporating it in most trauma pt's.  The FAST was positive excellent...now lets go to the OR??  or not...pt pressures were still in the 60s even with resuscitation. Blood was not readily available. Typically this would result in immediate OR intervention in the US, but the team felt that his head injury was too severe, and his quality of life would have been poor...watching resuscitation efforts/interventions stopped in this pt was a bit unsettling.
 I have been trying to understand the scenario from the Rwandan physicians point of view.  A part of me understands, but still a very difficult pill to swallow.

Until next time...      

~Phindile Erika Chowa,MD
 PGY 3
Emergency Medicine Resident, BWH/MGH

Like Us

Blog Archive