Medical News Blog Information

Showing posts with label Healthcare workers. Show all posts

South Korean MERS cluster keeps growing..

version 3.
This cluster of hospital-related infections in South Korea has now reached 64 Middle East respiratory syndrome (MERS) cases. And no camel meat or milk, no route of ingestion yet fond in fact not even a camel to be seen - except the ones quarantined in the South Korean zoo - I can't even....

Anyway, thanks to a week long internet outage in my house (yes, I do these blogs from home) I've been unable to blog on any of this. 

Surprisingly though, after a week, the cluster is still going pretty strong. The recent tallies include 6 cases then 5, then 5, then 6, 9 and last night 14. These include 5 deaths (10%). 

As you'll see from the first 11 cases I've plotted below, this is similar to a bunch of incidents we've followed in Saudi Arabia in 2013 to today (Hafoof seems to have a pretty good cluster going at the moment). They have usually been the result of poor infection prevention and control creating a perfect storm of circumstance for viral spread. 

Timelines of the first 11 cases of MERS-CoV infection in South Korea.Click on image to enlarge based on World Health Organization and  FluTrackers information with help from this timeline. Hospital names have been published here and here - I'm not sure if this is how they are ordered so please consider this a work in progress.
Click on image to enlarge

It's looking like this will be the case in South Korea too. 

A couple of interesting things to note:

  1. Cases are still popping up - a month later
  2. A viral genome sequenced in China (ChinaGD01), from a South Korean case that flew out of South Korea to Guangdong, does not show any obvious genetic differences compared to other MERS-CoV genome sequences. Its sequence identity falls in the range that we can fit around all the MERS-CoV genomes - whether from humans, camels, from Saudi Arabia, Qatar or the United Arab Emirates, 2012 or 2015.
  3. MERS cases in South Korea are tightly linked to hospitals - healthcare workers feature prominently as do other "close contacts" including relatives who stay at the hospital to help care for their loved ones. There are no indications of escape outside those hospitals so the closing of schools, the wearing of masks (which don't cover eyes) and the increased border measures offered to North Korea have no support from science or facts
  4. Some incubation times are pretty short - just 3 or 4 days between exposure (in whatever form that is taking) and symptom onset - yet we haven't seen any not-so-close contacts come down with infections, despite that same time frame having passed long ago for them.
    Spread of virus is not very different to what we've observed in Saudi Arabia for 3 years
  5. A few people have called the index case a "super-spreader" because of all the contacts he's had that have developed MERS (what about those who haven't developed disease by the way, are they being tested?) - I've come to loathe that term. It lazily defines the person as super-spreader while ignoring the context in which that person has been managed - namely whether infection control measures are well used, or in place at all. A super spreading event I like a little more - but even that makes something, special scary or different  out of what may be something completely normal in infectious disease biology
  6. Testing times are all over the place - in just those first 11 cases it could be 9 days before a test result confirmed MERS-CoV infection. Therein may lie a reason for why MERS cases are still appearing now - no-one knew then, nor for a decent while, what they had. Although...they did know that they had an acute respiratory infection and I can't for the life of me work out why these viruses seem to get away from us time and time, and time again. Well, yeah I do - it's because people.

"Are we ready for the next pandemic?" is a question that has been asked a lot since the peak of the peak of Ebola virus disease epidemic in West Africa. The answer is that there is no way in a million years we're ready.

Version history.
  • v2-fixed graphic's transparent background & changed case tally from 50 to 64
  • v3-added in hospital names and a few more cases.


MERS-CoV snapdate on canaries...

MERS-CoV detections among healthcare workers (HCWs)

HCWs are akin to the canary in the coal mine - when HCWs get sick with a particular bug, this can signal that the bug may well be more active in the the wider community. 

This graph looks at the canaries and suggest that there has been a relatively long period in which they have been getting infected.

Healthcare workers positive for MERS-CoV over time.
Some reported or hypothesized clusters and outbreaks are flagged.
Click on image to enlarge.

A quick look at my database shows that most of the MERS-CoV-positive HCWs reported since October have been from Riyadh in Ar Riyadh region and Taif in Makkah region. 

Just before that, in early September, there were 2 HCWs from Jubail in the Ash Sharqiyah (eastern) region. 

If we look at the new time-based occurrence heatmap I have on my MERS-CoV static page here, the recent group of HCWs come from the areas with most cases. No big surprise there. Perhaps more surprising is why these HCWs are, presumably, still acquiring there infection in hospital settings given eh attention that infection prevention and control practices had, especially (before?) during and after the Jeddah outbreak last year.

A recent paper from Profs Drosten and Memish speaks to this topic of infection control and hospital spread of MERS-CoV a little.[1] 

It reports finding a 40-year old female (40F) nurse who, despite MERS-CoV being such a wimpy transmitter between humans, became infected after attending an infected patient. 40F did not perform any aerosol-generating procedures  but also wore only a surgical mask and gloves - it reads as though she was not fully protected against droplet, and certainly not against airborne, exposure. 

The 40F HCW then went on to shed virus for a 42-day period as determined by MERS-CoV specific RT-PCR. She was not ill during this time. Hard to contain much?

So with all that in mind, it's no longer hard to imagine how spread of MERS-CoV virus occurs within, around and between hospital settings. Also helps to explain how some of the new cases might seem strange - if not testing for subclinical or asymptomatic cases as a routine. I recall that in Saudi Arabia routine testing of milder cases is not occurring, but I cannot find a source for that recollection just now so I stand to be corrected (please send if you know if a reference that alludes to that).

A couple of quick questions spring to mind:
  1. Just how widespread is this lengthy shedding period?
  2. What does this say about how mild a virus MERS-CoV is when comorbidities are not a factor?
  3. What role do genetics play in the host's containment and clearance of MERS-CoV infection?
Heatmap of MERS-CoV detection by date and region
within the Kingdom of Saudi Arabia
Click on image to enlarge.
Reference..
  1. A Case of Long-term Excretion and Subclinical Infection With Middle East Respiratory Syndrome Coronavirus in a Healthcare Worker. Manal Al-Gethamy, Victor M. Corman, Raheela Hussain, Jaffar A. Al-Tawfiq, Christian Drosten and Ziad A. Memish.
    http://cid.oxfordjournals.org/content/early/2015/01/01/cid.ciu1135.long


Ebola virus, HCWs infections and personal protective equipment..

Co-authored by Dr Katherine Arden.

No one could offer anything but our deepest and most heartfelt thanks and a feeling of pride in the selfless, essential and humanitarian work being done by healthcare workers (HCWs), both local and international, in West Africa.

But they have paid a high price for this work, as they always do in emerging disease outbreaks.


WHO Ebola virus disease
numbers up to
14-Sept-2014
Of the >5,300 people reported as infected by the West African variant of Zaire ebolavirus (EBOV) to date, around 315 have been HCWs. Both numbers are very likely an underestimate. Half of the HCW cases have died. I don't know just how many HCWs there are in Guinea, Liberia and Sierra Leone who are dealing with the EBOV outbreak. I do know that these deaths are as horrible as each of the losses among non-HCWs, and are also worrying for those trying to recruit the many more HCWs needed to expand care of ill patients.


This week a commentary article on the Centre for Infectious Disease Research and Policy (CIDRAP) website delves into this issue by suggesting an improvement to HCW respiratory protection.[1]


Two quick things first:

  1. The World Health Organization (WHO) defines human transmission of Ebola virus as being by direct contact (between mucous membranes or a break in the skin and the blood and other body fluids of an infected individual via physical contact or by wet material being propelling onto mucous membranes or skin breaks) and by indirect contact via contaminated surfaces.[3,4]
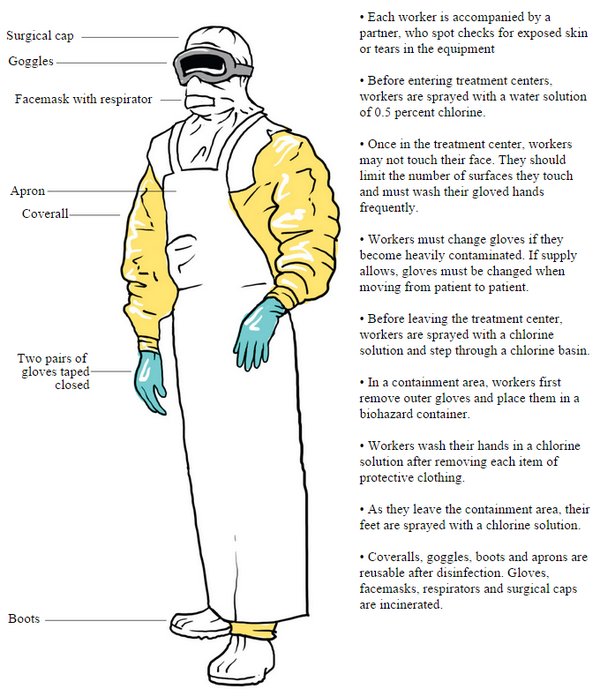
  2. When dealing with patients, the WHO recommends wearing gloves, a disposable impermeable gown to cover exposed skin, a waterproof apron over any gown that is not impermeable or when undertaking strenuous activity, facial protection to prevent splashes to the nose, mouth and eyes including a medical mask + eye protection (visor or goggles) or a face shield and medical mask.[3]
The CIDRAP article's authors claimed a belief that there is scientific and epidemiologic evidence that Ebola virus has the potential to be transmitted via infectious particles. Unfortunately they don't make a convincing argument to support their belief-nor could they, since no data currently exist to for any claim that an Ebola virus is transmitted between humans by an airborne route. So we're left with a commentary based on those beliefs, and some speculation.

Some collaborators and I wrote about Ebola virus not being an airborne virus based on what we know and what's been done to answer this question before.[2] I'll first add that if it were an airborne virus, we would likely be seeing many, many more cases-"Compared to this Ebola outbreak, the H1N1 swine flu had already spread to an estimated 10,000 times as many people in its first 10 months" noted United Kingdom virologist Ben Neuman.[13] H1N1 being an influenza A virus; a real airborne virus. In our post, we noted that big wet droplets (part of an "aerosol"-a messy term that may not be well understood by the public...or some scientists...that includes big wet droplets and small rapidly drying droplets) can be propelled at a mucous membrane or fall to the ground to contaminate surfaces.


A schematic of the makeup of an "aerosol".
From [2]
Big wet propelled droplets can contain infectious Ebola virus and are included in the established risk messaging. Hence the need for droplet precautions.

We also know that from every human aerosol, after the heavy larger droplets fall to the ground or impact on a surface, the remaining lighter droplets very quickly dry to form droplet nuclei (these can be gelatinous, gooey, or water-free). It's these droplet nuclei that can linger for hours or more in the air. We know that droplet nuclei can be made to contain infectious Ebola virus under lab conditions[8] thus droplet nuclei produced by an infected human may contain Ebola virus. We can't say with certainty that they do or do not. However, as far as we have been able to tell, infection of humans and resultant disease from inhaling lingering droplet nuclei, has not occurred. And when an airborne route was investigated using infected and uninfected non-human primates housed nearby but without direct contact, no infection via an airborne route was found to have taken place.[9]


When putting one's faith in the belief that a different piece of PPE will prevent or significantly reduce HCW infections, one has to wonder if that will empower a false sense of security among HCWs in the field where the infections are happening. Most of the studies looking at aerosol of Ebola virus do so in temperature and humidity-controlled laboratories with lots of lab grown virus.


And relying on one added component raises a few questions for me:

  • Could the faith in this one extra precaution threaten the very important, meticulous care required when donning, using, and removing contaminated PPE-of any sort?
  • What role does a lack of the basics, like soap and clean water [10], play in HCW infections?
  • Could an additional extra safety measure really have a major effect on reducing the known risks involved with treating Ebola virus disease (EVD) patients, such as the long hours, tiredness, the constant and pervasive tension of imminent exposure, the oppressive heat, delirious and sometimes violent patients and the ease with which one can self-inoculate?[6]
  • Does the extra safety measure even have a role in reducing risk associated with HCWs who are unknowingly infected while not wearing PPE?[7]
How much do the things listed above, mostly unrelated to having a hi-tech battery-powered breathing apparatus on your hip, contribute to the tally of HCW infections?

Glaringly, the authors overlooked mentioning that early on, many HCWs may have had few or no masks at all and few other essential barriers such as those listed by WHO above, to protect against direct contact. They also did not mention the lack of HCW training in the use of any of that equipment if available, and did not highlight the lack of experience HCWs had dealing with EVD patients. These HCWs had (and may well still have) direct contact with very ill EVD cases, and got infected. What fraction of HCW infections resulted from absent or incomplete PPE and training versus the HCWs that they believe became ill while wearing full droplet precaution PPE?


Embedded image permalink
MSF designed suit of PPE.
Graphic tweeted by the
Washington Post.[5]
Others have also made note of the disparities between the imagery of a biosafety level 4 (BSL4) laboratory researcher working in a negatively pressurized, airlocked laboratory within a tethered, airtight suit (probably unnecessarily high precautions [13]) versus highly biocontained single patients being shipped home on dedicated planes (kept somewhat contamination-free using isolators) to rich nations for specialized support and treatment versus M�decins Sans Fronti�res (MSF) workers who use respirators (specialized face masks that fit more snugly and contain more layers to better filter what is breathed in) instead of surgical masks versus the WHO recommendations of standard precautions which include a surgical mask. Notably, the WHO recommendations vary according to the type of risk one is exposed too [see pg 96-7 96 of the 113 pg PDF at [3]).[10] There clearly is a range of thinking and messages here. But equally, there are a lot of different applications to cover, and no way for every need to be specifically catered for by one guideline. If everyone could agree on such a thing anyway.

I share the concern of many over the deaths of HCWs in West Africa. They may still be unnecessarily exposed to virus due to the lack of enough PPE. They may not have enough training to understand how easy it is to become infected. They may not be given the message that during an EVD outbreak as monstrous and different as this one, many heavily populated areas have been included for the first time resulting in very real risks of infection occurring outside the hospital setting, not just inside it. There are also real risks of infection in supposedly EVD-free hospital settings like maternity wards.[11] There are many, many non-airborne related risks for HCWs.


We freely admit that we are not trained in the use of PPE for treating Ebola patients; just for working with actual respiratory and blood borne viruses in PC2 & PC3 laboratory settings, respectively. Still, some may find this post irrelevant.
By all means stop and read that disclaimer on the right about this blog not providing medical advice. You come here of your own free will and this blog is not part of any Organization's reference list when they write PPE guidelines...because it's a blog.

But for what it's worth, I would follow the MSF lead if working in the battlefield of a 100+ bed treatment facility. In an ideal world with unlimited and readily available resources, a more roomy and breezy head covering that allows patients to see your face and which can be worn for longer periods would be useful. You can see an image, provided by 3M, of this battery-powered air-purifying respirator (PAPR) accompanying the CIDRAP post.


However....first and foremost, and well before we get to this level of hair-splitting based on speculation and belief and no evidence of an airborne virus-I'd be wanting to make sure there was a minimum level of disposable PPE actually available for use by every HCW and the appropriate education about how to use it and about all the risks for acquiring EBOV infection.

Reasons for HCW infections are many and varied. As much as we may believe or wish it were so, no single act or change will circumvent these risks nor these infections.


References..

Snapdate: MERS-CoV in HCWs and those without symptoms

 Another quick chart update.

This shows what has been happening with healthcare workers (HCWs; Figure 1.) and asymptomatic outcomes of MERS-CoV infection (Figure 2) over time, around the world.

Figure 1. Healthcare workers shown accumulating over time (pink mountain; left-hand y-axis) and as a proportion of total MERS-CoV detections each week (pink dots linked by dashed lines; right-hand y-axis, percentage). I've also added in a cumulative average (HCWs each week divided by accumulated MERS-CoV detections at that point; right-hand y-axis, percentage)
Click on chart to enlarge.


Figure 2. MERS-CoV-positive people without signs or symptoms of illness. Numbers are shown accumulating over time (orange dots/line; left-hand y-axis) and as the number each week (blue dots/line; left-hand y-axis). I've also added in the proportion of all MERS-CoV detections in that week ,who were described as being asymptomatic (grey bars; right-hand y-axis, percentage).
Click on chart to enlarge.

This is all at the mercy of publicly available data of course, and if you've ever read this blog you'll know what I think about the quality of that for MERS! If not, read through past posts like these ones here, here or here.

MERS-CoV among healthcare workers: no longer identified or the end of a hospital cluster?

Just looking at @maiamajumder's vast array of MERS-related charts on Twitter and had a thought.

She and I and others have been wondering for a while if perhaps the Kingdom of Saudi Arabia's (KSA) Ministry of Health (MOH) reporting has decided to simply no longer identify healthcare workers (HCWs) as such. That would not be the strangest thing to occur with these data, believe me (deaths that have been "previously reported" that actually haven't, people who were discharged from hospital who were previously not described as being hospitalised, and of course, some instances of HCWs in KSA being identified as MERS-CoV positive by their country of origin and not by the KSA MOH). Perhaps not identifying HCWs is a way of attempting to stop pointing to what was a huge problem in infection prevention and control just last month?

But perhaps that is not entirely what is happening. 

Perhaps there is another reason and there may be some precedent to support it; HCW numbers have in fact realistically decreased because they are no longer being infected as often. Why not? Perhaps because April's Jeddah hospital-based MERS-CoV outbreak is under control. Have a look at the chart below. Some things to note afterwards:


Click on image to enlarge
  1. HCW numbers have stopped accumulating so rapidly. That mirrors total MERS-CoV detections of course. See some recent posts on the now receding wave of April's MERS surge here and here.
  2. The precedent I mentioned? When the Al-Ahsa hospital-related outbreak stopped in May 2013, so did the number of HCW positives/week dropped away. 
  3. There have clearly been a bunch of other HCW peaks which may also have been related to hospital-clusters that were not so obviously publicised (I'll have a loo over this some time in the future). Those spikes of HCW infections have narrower bases and higher peaks than does the Jeddah outbreak, so perhaps that can be used as an indication of them being short-lived clusters that were better controlled than Jeddah. Not rocket science I guess and probably stating the obvious to the experts out there.
  4. Infections in HCWs serve, as we already know, as a kind of sentinel system for identifying a spike in overall cases since more severe disease shows its face in hospitals and most likely represents the presence of other cases out in the community. His statement is much more believable now that we ;can look back and know that milder signs and symptoms of disease, or none at all, do not infrequently follow MERS-CoV infection).
I hope that our original hypotheses - that the KSA MOH has quashed identifying HCWs - was wrong. Heading towards Hajj-2014, it would be best to be polishing the very tarnished reputation of of the KSA MOH on matters ;of communication, not further damaging it.


MERS-CoV cases continue steep climb thanks most to 2 healthcare-related clusters...

Click on image to enlarge.
Data are for lab-confirmed cases only, and 

from FluTrackers, Ministries of Health
and the World Health Organisation Disease Outbreak
News reports.
The Jeddah cluster | Jeddah | Kingdom of Saudi Arabia. 

It is the biggest of any of the clusters of MERS-CoV cases within the Kingdom of Saudi Arabia, MERS-central (0 to date. It has seeded at least 2 internationally exported cases (a fatal case in Malaysia and now a case in Greece). It totals 53 cases so far; the tally for this cluster began after the onset of illness in the first case, 6-Apr.

The paramedic cluster | Abu Dhabi | United Arab Emirates

Happening simultaneously and right next door is a cluster of cases that began 28-Mar. It stands at 14 cases as I compose this; most recent with an onset of 14-Apr.

These dates, starting points and information are all up in the air of course. 

There have been no solid answers from either site on how each cluster commenced, so we don't know the actual 1st case nor how they became infected, what their status is or what type of contact occurred (animal or human-to-human). 

We don't know how many cases are linked together or even whether the 2 sites are linked. We don't know whether these focal outbreaks are ongoing nor just how so many healthcare workers (HCWs) can be infected by a respiratory virus that was already well known to the region and its hospitals (Wk 109, 2.1 years since first MERS cases). 

We don't know if this outbreak is just bad infection prevention and control at some hospitals/among some people. We are all wondering how this has continued among HCWs as it seems to be? After a couple of confirmed cases wouldn't masks and gloves and gowns be standard fare - if they weren't already in the management of unknown acute respiratory disease cases? Whether a "super spreader" is involved or not, such measures should have prevented so many healthcare workers becoming infected shouldn't they? 

Is this MERS-CoV Mk II - now with the ability to transmit efficiently and rapidly (before extra prevention measures are in place)? We have no MERS-CoV sequences to answer that. Spike gene sequences would at least help us understand he virus aspects? I don't really care about complete genomes-they are for phylogeny more so than public health; changes in Spike yielded information of value in the SARS-CoV event and for coronavirus in general, and could do so again. Just sequence that region guys! Do it quickly and release that info now. It's something informative. Don't wait for a scientific paper. Start a blog and put the results on there. Not just in Arabic and then in English some time later; with Yemen, the Philippines, Malaysia and Greece picking up cases in the past week, these 60+ cases are not just a Saudi thing (although the case numbers say otherwise-but you know what I mean), it's global village thing. Just tell us what's going on with the virus! 

So many things we don't know. "So what?" you ask Go and Google "MERS SARS" and limit it to the past 24-hours. That's so what. The media are starting to heavily lean towards the "MERS is the next SARS" story again and that stirs up concern at many levels. Is that concern justified. At the moment who the heck knows??? If there is no change in Spike, while not the be-all and end-all for change in the virus, it will allow the experts to make comments that inform the media that may calm a rapidly progressing situation with economically damaging potential for the world, and the region.

For crying out loud Ministry of Health|Saudi Arabia, get ahead of this thing.

Sources...

  1. The world's greatest resource for tracking MERS-CoV cases, the FluTrackers line list
    http://www.flutrackers.com/forum/showthread.php?t=205075

MERS-CoV: Healthcare worker numbers are spiking...

One of several questions I have about MERS just now is whether there are in fact more healthcare worker MERS-CoV-positive cases occurring now compared to previously. It feels like there are.

Overall there are 50 HCWs listed in my database at writing. This is a database I maintain from official (WHO and the various Ministries of Health) data as well as FluTrackers' independent data collection; all of which are publicly available. For those who follow me, you will know that I often complain about the MERS data being incomplete. So take these charts as providing you with a good guide to the situation rather than an official document. You are reading a blog after all.

Click on image to enlarge
So here we can see a few ways of presenting the HCW figures. Let's step through them:

a) shows you the proportion of just HCWs with fatal MERS-CoV infection (PFC) and the proportion who survive (the majority; PSC)

b) identifies the PFC and PSC among all 242 MERS-CoV cases worldwide for comparison

c) reveals the proportion of all 242 cases MERS-CoV cases who are HCWs again, for comparison

d) shows you the a comparison of the proportion of all MERS cases that are HCWs (~21%) and the proportion of MERS-CoV-positive HCWs who died (~3%).

Click on image to enlarge.
So to look more closely at how HCW numbers have changed over time, and particularly how they have changed lately, I've created a chart tracking HCW numbers both cumulatively (the pink mountain with numbers on the left hand side) and as cases announced per week (the purple dots, with numbers on the right-hand axis).

Sure enough, we have seen a big jump in the number of HCW cases in just the past week. In fact, Week 108 (Week starting 7-Apr) has been the biggest week in the 2-year history of MERS-CoV [however, see my caveats about case dates from my post earlier today]

There were few MERS cases at all in 2012 but in 2013 they took off in April and peaked in September (I'll plot these numbers for comparison in my next post). Since May-2013, HCW numbers have been spotty without any obvious pattern...to me at least. 

So that leaves the questions of whether we are also seeing more asymptomatic cases recently and whether the age is trending towards a younger value?

The ultimate question of course is why are things changing?

Healthcare workers may stay on the job when ill and can be shedding viral RNA...

In a prospective study in the journal Infection Control and Hospital Epidemiology, Esbenshade and colleagues described their analysis of 319 samples from a cohort of ill (119) and asymptomatic (200) healthcare workers (HCW) serving inpatients at Monroe Carell Jr. Children�s Hospital at Vanderbilt (MCJCHV) in Nashville, Tennessee, during Nov 16 2009 - April 16 2012. 

This was a 20-week period when influenza was expected to be circulating. Most HCWs had been vaccinated against influenza A(H1N1)pdm09 virus

Nasal (not nasopharyngeal) swabs were collected by a trained staff member every 2-weeks, with extra swabs taken if a period of illness arose in the meantime. Nasopharyngeal swabs (NPS) do yield higher proportions of viral detections but are not pleasant and may have caused study drop-outs among the volunteers so they were not used. 

Influenza viruses, respiratory syncytial virus, rhinovirus (RV), human metapneumovirus (HMPV), parainfluenzavirus (PIV), endemic coronavirus (HCoV), adenovirus, bocavirus and enterovirus shedding was represented by the presence of viral RNA detected using a commercial PCR assay (MultiCode-PLx-RVP). An internal control target, �-actin, was included to monitor the integrity of the extracted nucleic acids. 

A PCR positive is assumed to represent shedding of an infectious virus.

The findings are relevant to my recent rant on prospective testing (seek and you shall find). Some key findings were:

  • HCWs often worked despite being ill
  • The strongest and most statistically significant risk of finding a virus in a subject was associated with that subject being symptomatic (I'm going to be writing about asymptomatic infections in the coming weeks)
  • Only 42 specimens were positive for a virus - mostly RV (33) followed by PIV (4), CoV (4) and HMPV (1) - lower than expected
  • Younger age was positively associated with viral shedding while the subject's role as a nurse or a physician was not
  • 15% of RV detections were made from asymptomatic subjects - 25% of PIV or HCoV (OC43 and NL63) detections were from this group.
  • 85% of RV detections were from symptomatic (ill) subjects
The authors conclude that HCWs should consider avoiding patient care duties while ill and that institutional policies should be updated to reflect this need to limit hospital-acquired infections.

When you test for things, its amazing what gets found and how this can impact on policy, understanding of infectious disease transmission and improved patient management. 

This is also a timely reminder that issues around infection prevention and control (IPC) are in no way limited to the management of newly emerged viruses like H7N9 or MERS-CoV. IPC is a problem the world over and it requires constant vigilance to stay ahead of. I commend the authors for this study.

Like Us

Popular Posts

Blog Archive