Medical News Blog Information

Toward Emergency Department Integration in Ethiopia


In the dark of the night, our plane descended. A galaxy of yellow and orange house lights swarmed below, drifting closer to my pocket of airplane window. Twenty hours of travel (including two brief layovers) was nearly over. Complimentary glasses of red wine (for the circadian adjustment) had done their trick, and our wheels skidded down on cool Addis Ababa tarmac like a reunion of old friends.

Just three years previously (in November of 2011) I made my first trip to Ethiopia, as part of a multinational study assessing medical and nursing students� migration intentions. At that time I partnered with senior educators in Addis Ababa University�s School of Medicine and worked closely with senior and junior students alike, making quick and close friends at all levels. Ethiopia had felt a strange and unfamiliar place to me then�far different in culture, climate, history and language than any sub-Saharan African place I had ever visited. Now three trips later, however, it was almost a second home, my friends here some of my dearest, and the culture and customs no longer new.

As I waited in line for a renewed visa, watching disembarking passengers bolus past outnumbered Ebola screeners, excitement and impatient apprehension both swelled as I began to unlock the mental list of immediate �to-do�s� needed to jumpstart the upcoming three weeks of work. No longer studying health professional student migration (as I had my first two trips) or working clinically in the Emergency Department (as I had my third trip), my goal this trip was to forge a network of Ethiopian Emergency Departments in order to aid in multicenter data collection and analysis, and national and regional policy reform.

As elsewhere across sub-Saharan Africa (and, in fact, throughout low- and middle-income countries), the importance of emergency care is growing. And while most Disability-Adjusted Life Years (DALYs) in sub-Saharan Africa are still lost to lower respiratory tract infections, diarrheal disease, HIV/AIDS, and malaria (by Global Burden of Disease data), the burden of traumatic injury and acute presentations of non-communicable ailments is rising.

Ethiopia, in particular, finds itself in a unique situation. With the 13th highest population in the world (second in Africa only to Nigeria), it also has both the largest proportion of rural inhabitants (80%) and the highest rate of urbanization (5%) of any of these most populous countries. But that�s not all. Among these most crowded nations, Ethiopia continues to boast one of the highest per capita GDP growth rates. In other words, Ethiopian cities are growing faster than in any other most populous nations (urbanization rate). Additionally, they will likely continue growing for longer than anywhere else, given the proportional and absolute size of the rural population, and they are filling with people who now have somewhat more money than they did, say, a decade ago. This money is often sufficient to afford slightly less healthy lifestyles (diet, cigarettes, etc.)�but not ample enough for medications to control the corresponding resulting chronic diseases. While these trends are familiar across Africa, it is in Ethiopia where a �perfect storm� of demographic and economic realities have rendered them most pronounced in both absolute and relative terms.

 For Ethiopia, the encroaching high tide of emergency care need represents both an immense crisis and an unprecedented opportunity. For a nation so historically rural, the urban health system capacity�including its emergency care capacity�must be rapidly expanded if it is to have any hope at absorbing the influx of demand. But precisely because so much growth is needed all at once, there is great advantage to undertaking it in a coordinated fashion. Indeed, it is in hopes of helping coordinate the emergency care data collection systems that I return to Ethiopia.

My first few days consisted of logistical essentials: buying a phone, buying a SIM card, buying a second SIM card when the first SIM card didn�t work; checking into a cheap hotel, moving to a second hotel with more reliable internet and closer proximity to the hospital; scheduling meetings, preparing documents for said meetings, rescheduling meetings, defaulting to back-up plans when rescheduled meetings fell through�. And finally came the opportunity to sit down with the Head of the Emergency Department (one of the hospital�s busiest men)�in a small hidden conference room tucked behind three bustling ED rooms. I handed him my proposal. We talked. Our meeting was brief; it didn�t need to be longer. We saw eye-to-eye�our mutual appreciation for the importance of this task fueling each other�s excitement. Without delay, he introduced me to an individual who would become over the next several days one of my closest collaborators�a young nurse
manager (A.Y.), recently trained in emergency care and critical care nursing and now working to coordinate referrals between Addis Ababa�s government hospitals.


As week 1 came to a close, I had spent many long days venturing with A.Y. and his team to all of the city�s government hospitals (as they coordinated referrals between them), confirmed data recording systems at each one, and developed a plan with A.Y. to standardize inconsistencies going forward. It was time for the next important meeting�with the Ministry of Health.

Over aromatic black Ethiopian coffee, we sat and pored through an intricate spreadsheet I had assembled on my computer late the previous night, summarizing the full week�s findings. The cool morning air bowed to midday sun, and we switched tables to keep talking. The lunch crowd came, then left. And still we talked through further details. Reviewing variables, considering how to improve collection of still others, discussing which additional ones might even be added going forward�and how, logistically, in a network of government hospitals with universal paper charts, to accomplish these tasks. Our work, at last, was finished. A team was formed. And week 1 in Ethiopia was complete, far more successfully than I could have imagined, thanks in large part to the Partners Centers of Expertise Global Health Grant.

Dave Silvestri, PGY-2
Department of Emergency Medicine
Massachusetts General Hospital
Brigham and Women�s Hospital
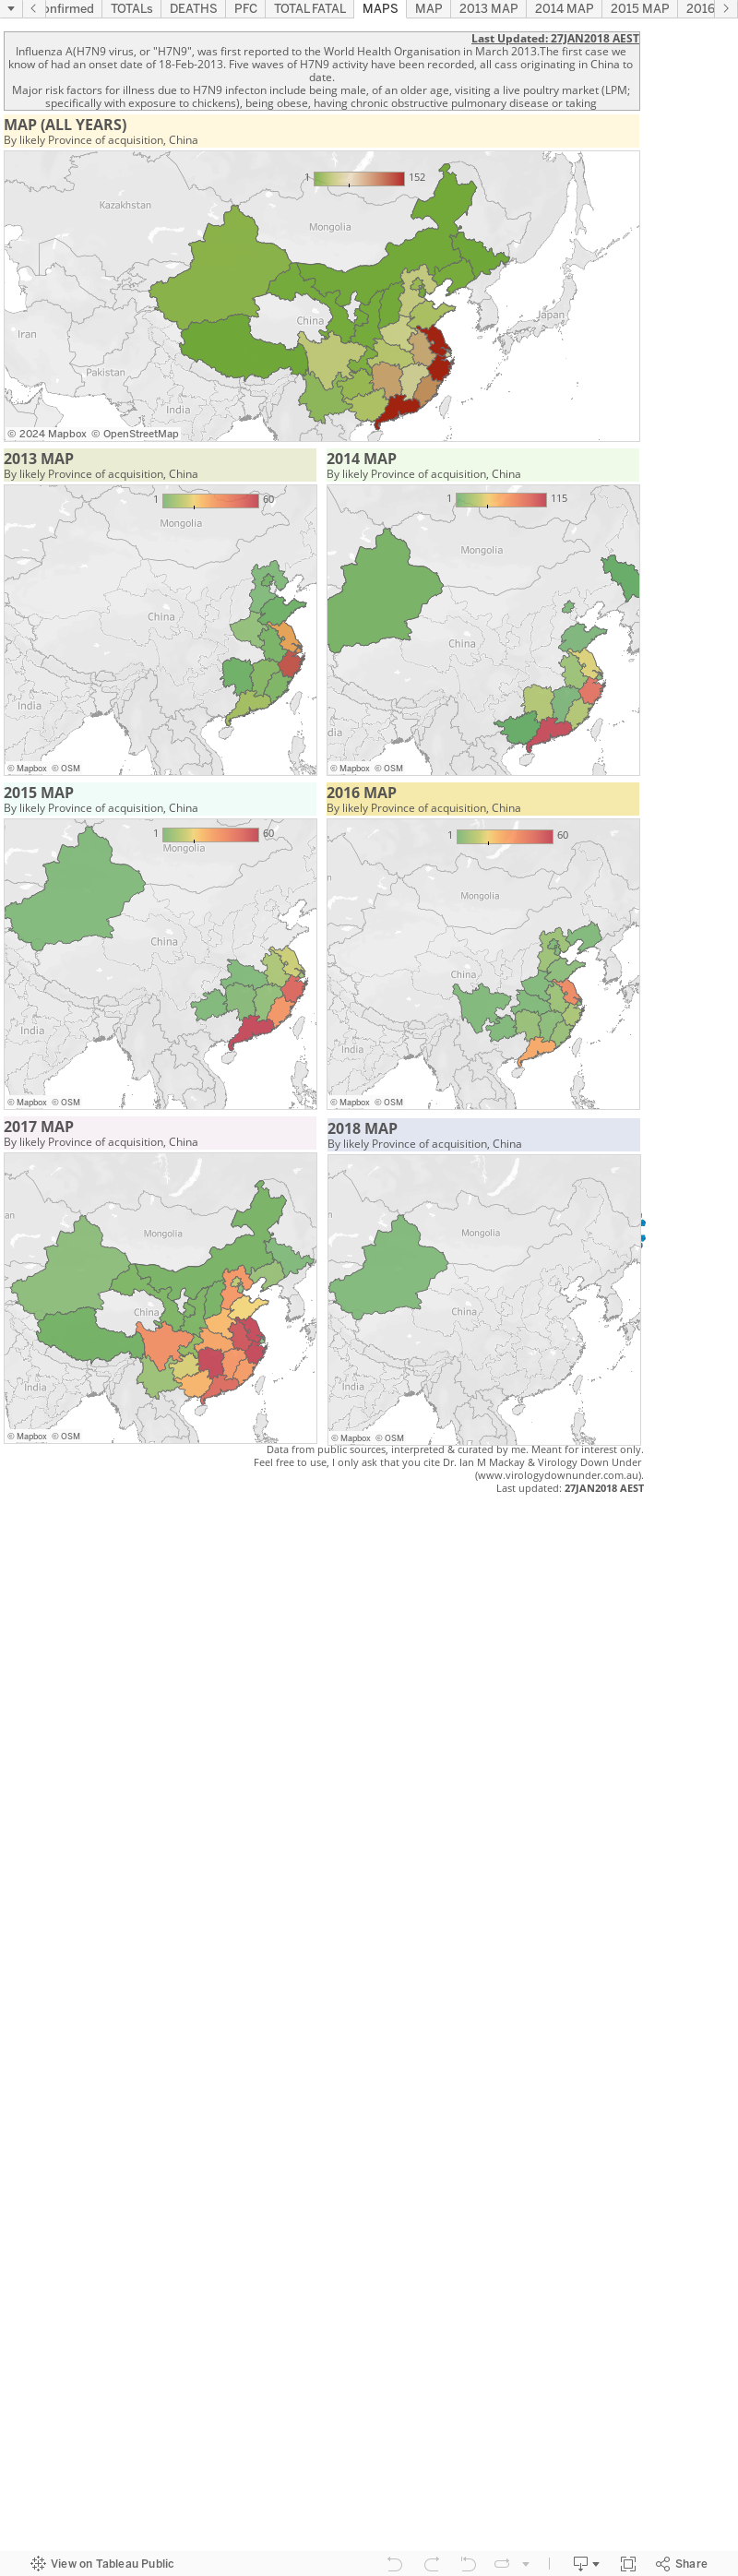

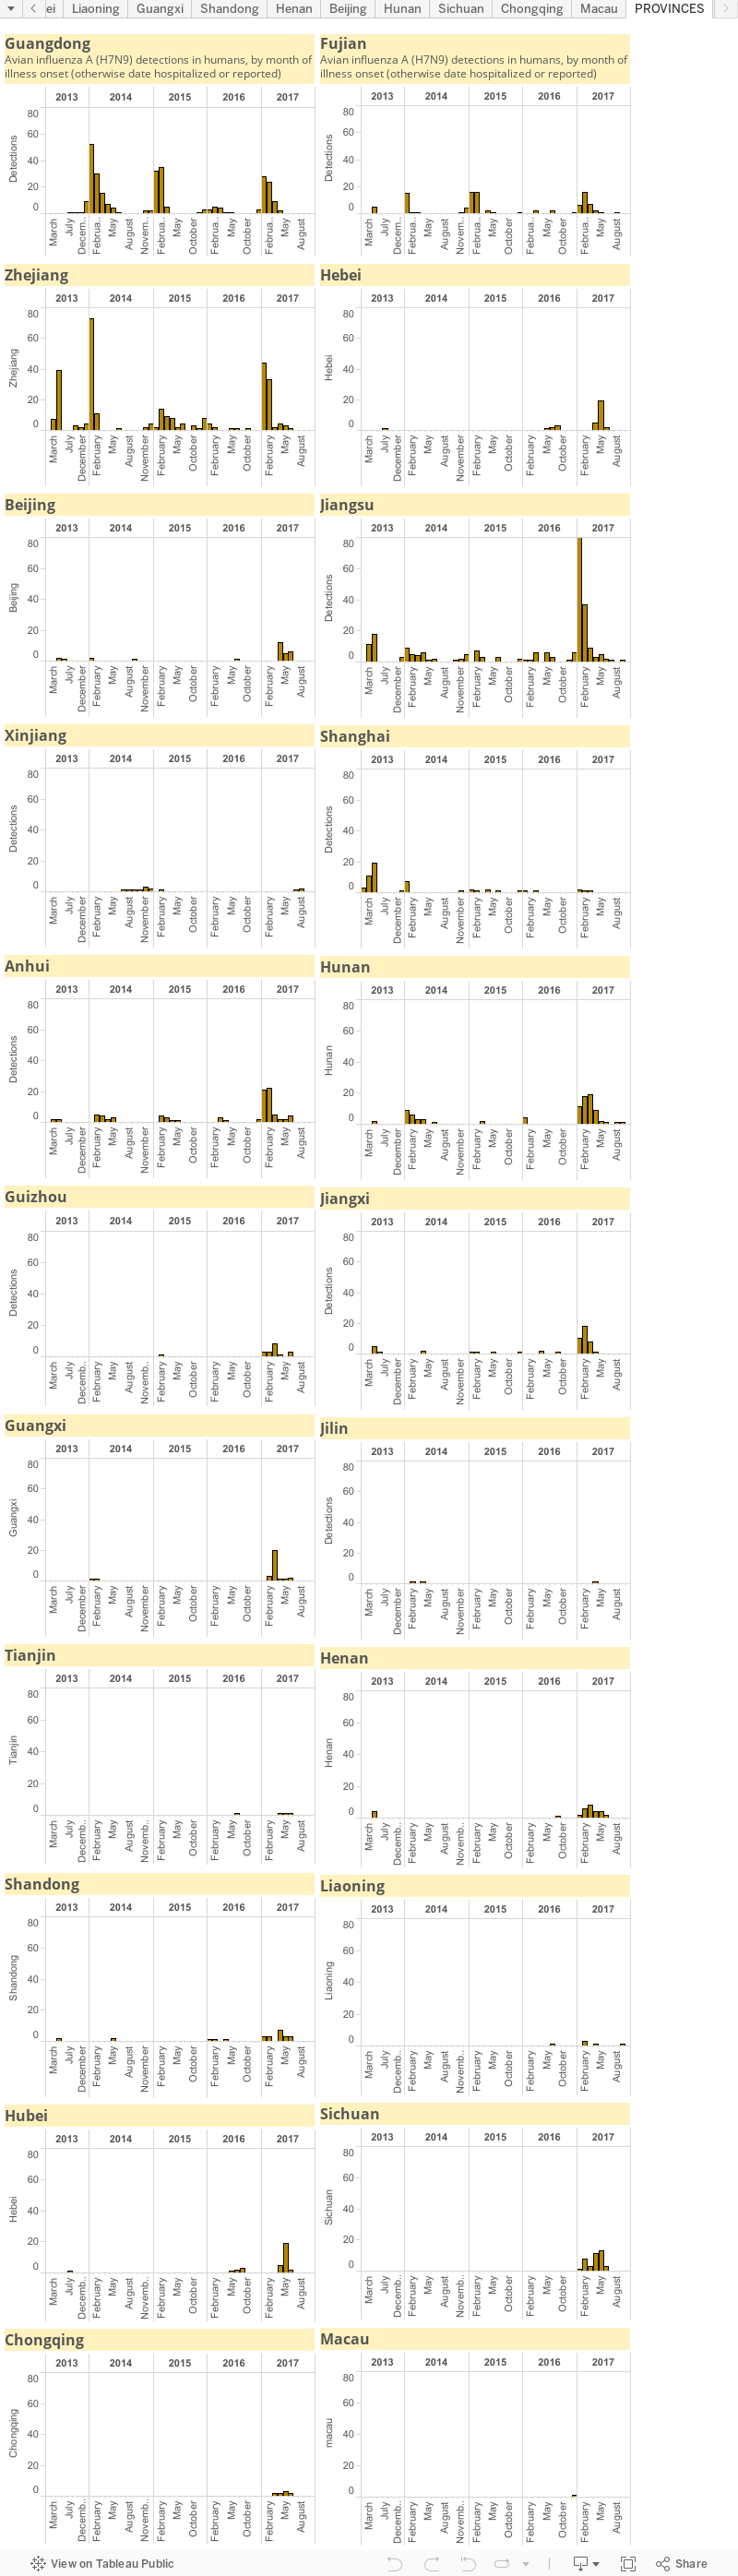
Influenza A(H7N9) virus: detection numbers and graphs...

This is a static page that will house my graphs of influenza A(H7N9) virus ("H7N9) numbers produced by the various Ministries of Health for the provinces and municipalities of China, the World Health Organization and FluTrackers.

They may take me a little while to get back up-to-date in this new format so stay with me. I will Tweet each update as I do for MERS-CoV and Ebola virus updates.

There is also an accompanying map page which for now is located here.


Reminders: 
  • The graphs above, as with all on VDU, are made for general interest only. They are also freely available for anyone's use, just cite the page and me please. The data can be downloaded by clicking on the "Download" link at the bottom-right of each dashboard. It may be that I have misinterpreted the language in the reports (sometimes a little tricky to wade through) or miscalculated some totals based on the way data have been presented.
  • In any outbreak, epidemic or pandemic caused by a know or emerging pathogen, the numbers presented publicly, and used in these graphs, are expected to represent only a fraction of all the cases that have and are occurring. This is just the nature of the imperfect biological'ness of these events.
  • I am only able to plot what is publicly available-you could do this too. No secret associations or back-room deals provide me with these data.

The bad the worse and the over-interpreted...

EVD case numbers between WHO reports. 
The World Health Organization (WHO) Ebola virus disease (EVD)case numbers that came out on 29-Oct were pretty big (see graph on the left). As if there weren't already enough new cases and deaths every 2-5 days, now there is this bolus of 3,562 cases added to the total. And a net change in deaths of -2? What the heck?  

Let's see if we can add some context.

According to a number of past WHO reports, a lot of effort has been going in to trying to collect data more effectively including improving the linkage of lab results to cases, cases to deaths, lab data to deaths and probably a million other things. 

Dr Bruce Aylward
http://www.who.int/dg/adg/aylward/en/
In the previous Roadmap SitRep and Roadmap update, the Liberian numbers did not move - they even had the same date. That was new and it was concerning because it suggested that reporting had been stopped or collapsed entirely. However this new large download of cases is in some way good news because it suggests reporting is working and the systems and processes are coping - although undoubtedly still stressed - again. 

The thing to be aware of is that these are not cases that have all been detected or all occurred since the last report 5 days previously. According to Dr Bruce Aylward, WHO Assistant Director-General, Polio and Emergencies, during a preceding media conference (and my thanks Martin Enserink for asking the important question; underlining is mine)..

In terms of the jump in the number of cases, one of things that we've talked about in the past on this is that with the huge surge in cases in certain countries, particularly in September and October, people got behind on their data.
They ended up with huge piles of paper in terms of cases, etc, and we knew and I actually said to you the last time, we are going to see jumps in cases at certain times that are going to be associated more with new data coming in but it's actually on old cases.
And a couple of days there were about 2,000 additional cases in, if I remember correctly, it was actually the Liberia case report but most of these were old cases because remember they got swamped a couple of months ago with a lot of new cases and just got behind on their data, so a lot of that is about reconciling new data.
If we look at sort of a seven day rolling average number of cases which have been around 1,000, just under that, about 900, there hasn't been a big change in that in the recent weeks.
So the 3,562 cases come largely from the past as well as the present. It's not that the sky has fallen in the past 5 days. Which is good news. But of course, that puts us back to "just" 1,000 or so Ebola virus disease cases a week. In other words, in just 1 week there are more cases than in any individual outbreak since 1976. 


The cumulative EVD case curve at 29-Oct
However, this week has seen a few articles and comments noting that the number of new cases in parts of Liberia seem to have fallen slightly. 

This seems to be a real trend in that there are fewer burials and more empty treatment beds and fewer cases found when sought in the community. Why there are fewer is not precisely known and it is far to early to rely on this yet. But we do know that there are better numbers of safe burials, better education, more experience with the disease, more help and facilities and more PPE comapred to when this started. 

The three countries with intense transmission still require a lot of help from us though - that urgency must not let up. Remember that cases had dropped a lot back in May - and now look where we are.  

If you can't get there in person to offer specialist help, and most of us cannot, keep bringing the issue to the attention of your country's leaders, learn about the virus and the disease from trusted sources and help teach others and head off ignorant comments, and donate some (some more) money to those groups who can make a real difference on your behalf (I've listed some great options here). 

Fighting the fire at its source is still the best way to help save lives in Guinea, Sierra Leone and Liberia and to stop new outbreaks from occurring in other countries.

References..

  1. WHO Ebola Roadmap SitRep#10
    http://apps.who.int/iris/bitstream/10665/137376/1/roadmapsitrep_29Oct2014_eng.pdf?ua=1
  2. Virtual Press Conference transcript
    http://www.who.int/mediacentre/multimedia/vpc-29-october-2014.pdf?ua=1

Point-of-Care Ultrasound Training for Emergency Medicine Residents in Kigali Rwanda

October 30, 2014

I am so grateful to have had the opportunity to join the PURE Team here in Rwanda and thank the Center of Expertise in Global and Humanitarian Health for making it happen.  PURE stands for Point-of -Care Ultrasound in Resource limited Environments and was created by a rock star former Harvard Emergency Medicine resident Dr. Henwood.  When Dr. Henwood gave a presentation on the impact of Ultrasound in resource limited settings her senior year, I knew that I wanted to not only perfect my ultrasound skills, but to also provide a useful skill to the practitioner abroad who sometimes may feel helpless when CT or Xray is not readily available.

Day 1
I survived a long trip to Kigali, Rwanda.  The view from the plane was amazing.  The landscape reminded me of my days as a child living in Swaziland.  I was picked up from the airport by one of the team members and given a short tour of the city before going home and crashing.  The people were wonderful and I even learnt a few greetings in the local language.

Day 2  We packed up the rental car to go to a district hospital about 2.5 hours away to give a training on Cardiac ultrasounds, FAST, and DVT ultrasound.  We drove up a windy road on a mountain ( mountains are very common here) where my heart literally wanted to jump out of my chest.  The view was amazing.

Unfortunately, the car broke down some where near the top of the mountain.  Within 30 minutes we had the local people call for the local mechanic.  The mechanic came on bike from Lord knows where and he diagnosed our car with an "engine problem" and called for the local tow truck to tow the car back to Kigali.


We paid about 300 US dollars to be taken back to Kigali Rwanda and to have the car towed-my pockets hurt still. It ended up being quite the experience, but somehow we had a wonderful day.  We met new people, saw a new place and broke bread together in the car.
After working in a few places in Sub-Saharan Africa one must be super flexible and adaptable, things happen and you must make the most of it.  I honestly had no complaints about this day.

Day 3
Okay finally work!!  We arrived at the University teaching hospital of Kigali at 8 am.  Our work is performed in the emergency and accident ward mostly, but other internal medicine, surgical and pediatric wards have requested to have scanning sessions for their residents.
 This ward serves a slightly different purpose than the emergency room in the US.  Most patients present from referring district hospitals and this can even be a matter of several days before arriving here.  I was told the role of the ED, is changing though with new emergency residents training in the hospital.  Our job is to teach and help facilitate scans with them and internal medicine, and surgical residents.  We in no way are here to take any role in patient care.

This day was busy, but apparently it gets more busy than this.  We had a number of scans in the morning. For example, we performed an ultrasound on pt who had known cardiomyopathy who presented to the hospital with shortness of breath.

The staff only had an xray from 1 month ago that they continued to refer to the size of the pt's heart.  For whatever reason, xray could not be performed that day.  We had the residents grab the US machine and look at the pt's lungs and heart.  He had bilateral pleural effusions, and diffuse B-lines likely representing interstitial edema.  His heart was globally dilated and had extremely reduced function.  The residents performed the scans and proceeded to treat the pt for a CHF exacerbation.

 We also had a trauma come in from the scene with GCS of 3.  One of the stellar training Emergency residents, ran the trauma.  A-B-C's initiated.  Pt airway was secured with ETT, He had a flail chest and decreased Breath sounds on the right and had a chest tube placed, and he was hypotensive and bradycardic.  His Pelvis was unstable.  The Emergency resident immediately called out for the US.  This was not typical in the past as part of the initial trauma evaluation, but the residents who are so excited about ultrasound have been incorporating it in most trauma pt's.  The FAST was positive excellent...now lets go to the OR??  or not...pt pressures were still in the 60s even with resuscitation. Blood was not readily available. Typically this would result in immediate OR intervention in the US, but the team felt that his head injury was too severe, and his quality of life would have been poor...watching resuscitation efforts/interventions stopped in this pt was a bit unsettling.
 I have been trying to understand the scenario from the Rwandan physicians point of view.  A part of me understands, but still a very difficult pill to swallow.

Until next time...      

~Phindile Erika Chowa,MD
 PGY 3
Emergency Medicine Resident, BWH/MGH

Why Ebola virus is not human immunodeficiency virus (HIV)

I'm not an HIV expert and only an Ebola virus hobbyist but let's see if we can list some things that are similar and different about these two viruses.

Some ways that Ebola virus and HIV are similar...
  1. Both are harder to catch than a cold. They do not spread through an airborne route.
  2. Both have lipid envelopes - Ebola virus is about 904-
    1,100nm long x 80nm wide whereas HIV is about 120nm around
  3. Both can be transmitted in blood, breast milk, and through sexual contact, being present in seminal fluid (HIV also in female genital secretions). For HIV the extent of the frequency of exposure and the viral load play during that exposure, play a role in the likelihood of infection; this is not well defined for Ebola virus.[1]
Some ways that Ebola virus and HIV differ...
  1. HIV is an RNA virus that goes through a DNA phase which allows it to hide in our cells while Ebola virus is strictly an RNA virus
  2. Ebola virus infects dendritic cells, monocytes, macrophages, endothelial cells, endocardium, kidney and liver cells but not peripheral lymphocytes while HIV primarily infects CD4+ lymphocytes and also dendritic cells
  3. They differ in the mechanics underpinning the way that they replicate themselves
  4. Ebola virus disease occurs very quickly whereas acquired immunodeficiency syndrome (AIDS) has a long latent period (although there is an earlier more acute disease)
  5. At writing, no antiviral or vaccines exist on the market for Ebola virus or Ebola virus disease; a range of drugs exist to slow or suppress HIV
  6. Ebola virus acutely kills cells, causes coagulation, organ damage and disrupts the immune response without lingering; HIV eventually becomes latent in the cells it infects, integrating with the genome
  7. Ebola virus has 7 genes, HIV has 9 and overlapping reading frames.
References...
  1. Principles of virology. Flint SJ, Enquist LW, Racaniello VR, Skalka AM.3rd Edition. Vol 2. Chap 6.

Mali makes it 6 countries in the West African Ebola virus disease epidemic

v2 251014

The 6th country in the West African outbreak to host a case of Ebola virus disease (EVD) in 2014, is Mali.

The case was a 2-year old girl who was symptomatic while still in Guinea.

She travelled with her grandmother >1,000km by public transport to Bamako (Capital city of Mali), setting out 19-Oct. WHO are treating the situation as an emergency; there were multiple opportunities for exposure. The case's mother may have died of EVD in Guinea and her grandmother may have travelled from Mali to Guinea to attend the funeral.


The case had contact with health services in Kayes, western Mali, on 20-Oct. She was referred and admitted to a paediatric ward of Fousseyni Daou Hospital 21-Oct with a fever of 39�C, cough, bleeding from nose and blood in her stool). Tests were negative for malaria but positive for typhoid fever. Pain relief was given but there was no improvement. 

Further tests confirmed EBOV 23-Oct at the SEREFO (Center for TB and AIDS Research) laboratory in Mali.

Samples are being sent to a WHO-approved laboratory for confirmation.

The girl has since died.[2]

The 2014 West African epidemic and Central African outbreak of EVD.
Click on image to enlarge. Feel free to use and share this map
(please attribute to this blog).

NB: Nigeria (19-Oct) and Senegal (17-Oct) were declared EVD free.
References..


    1. http://www.who.int/mediacentre/news/ebola/24-october-2014/en/
    2. http://www.bbc.co.uk/news/world-africa-29755443

    Like Us

    Blog Archive